Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
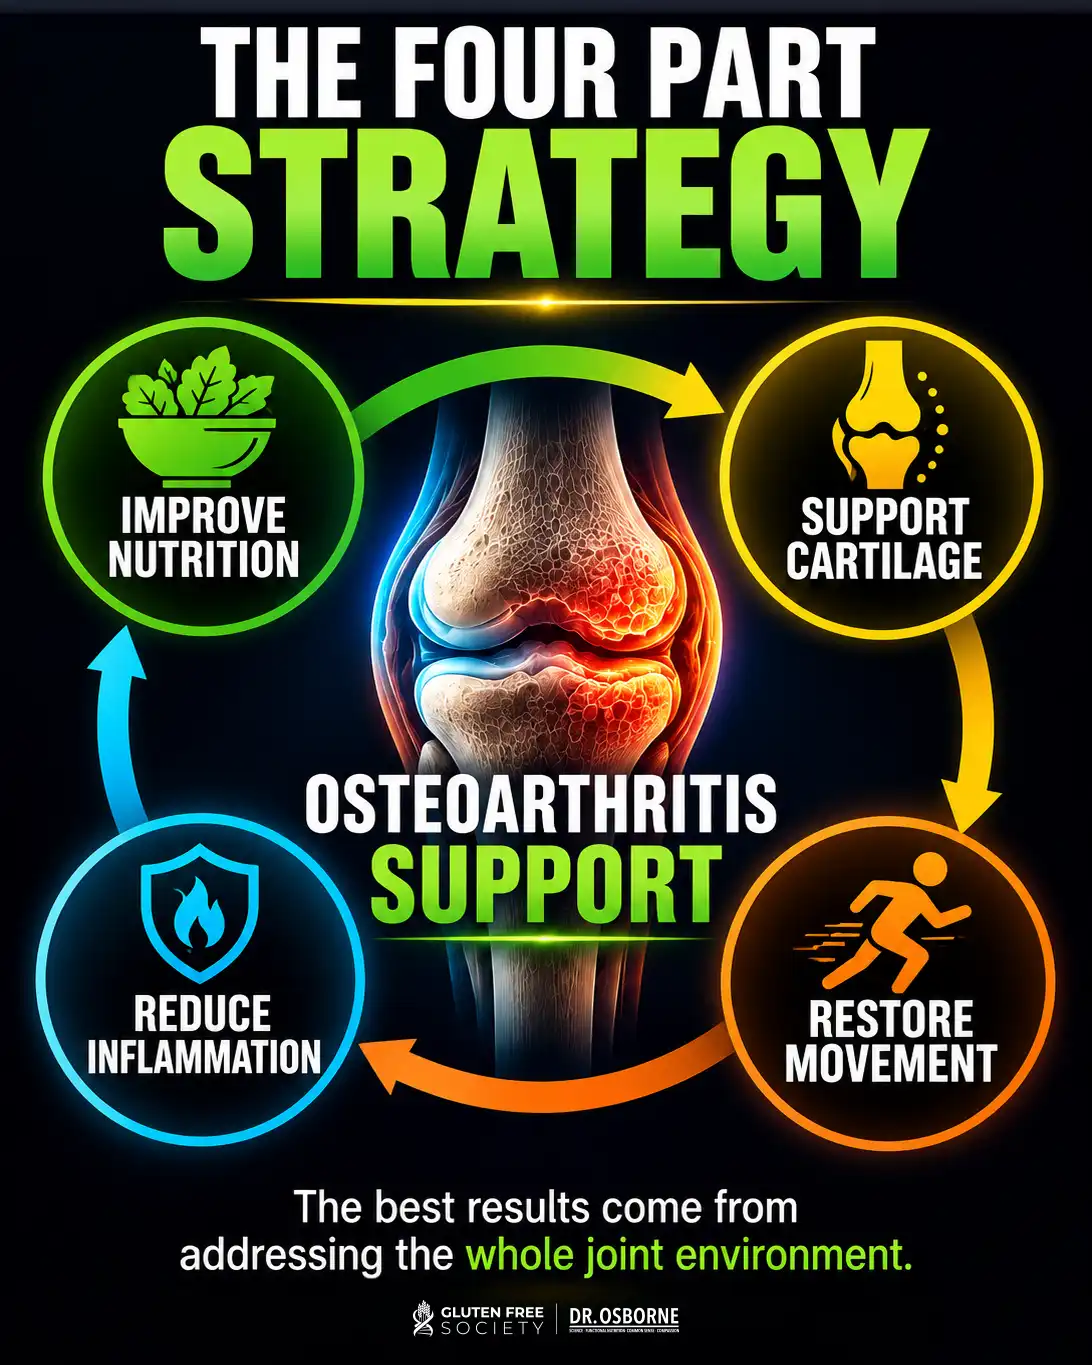
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
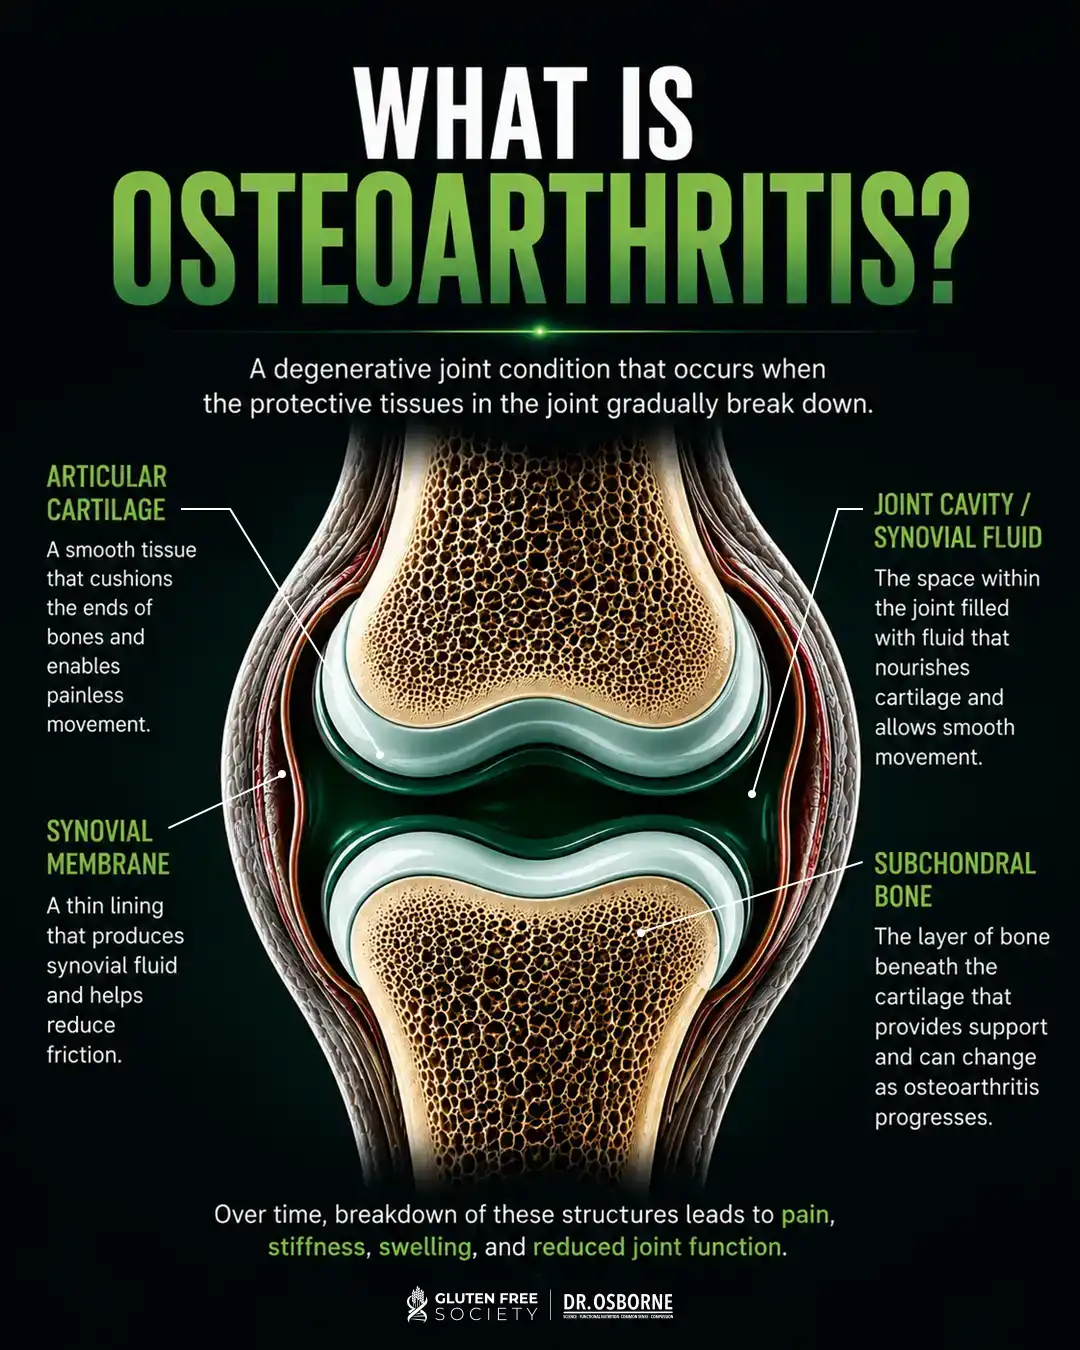
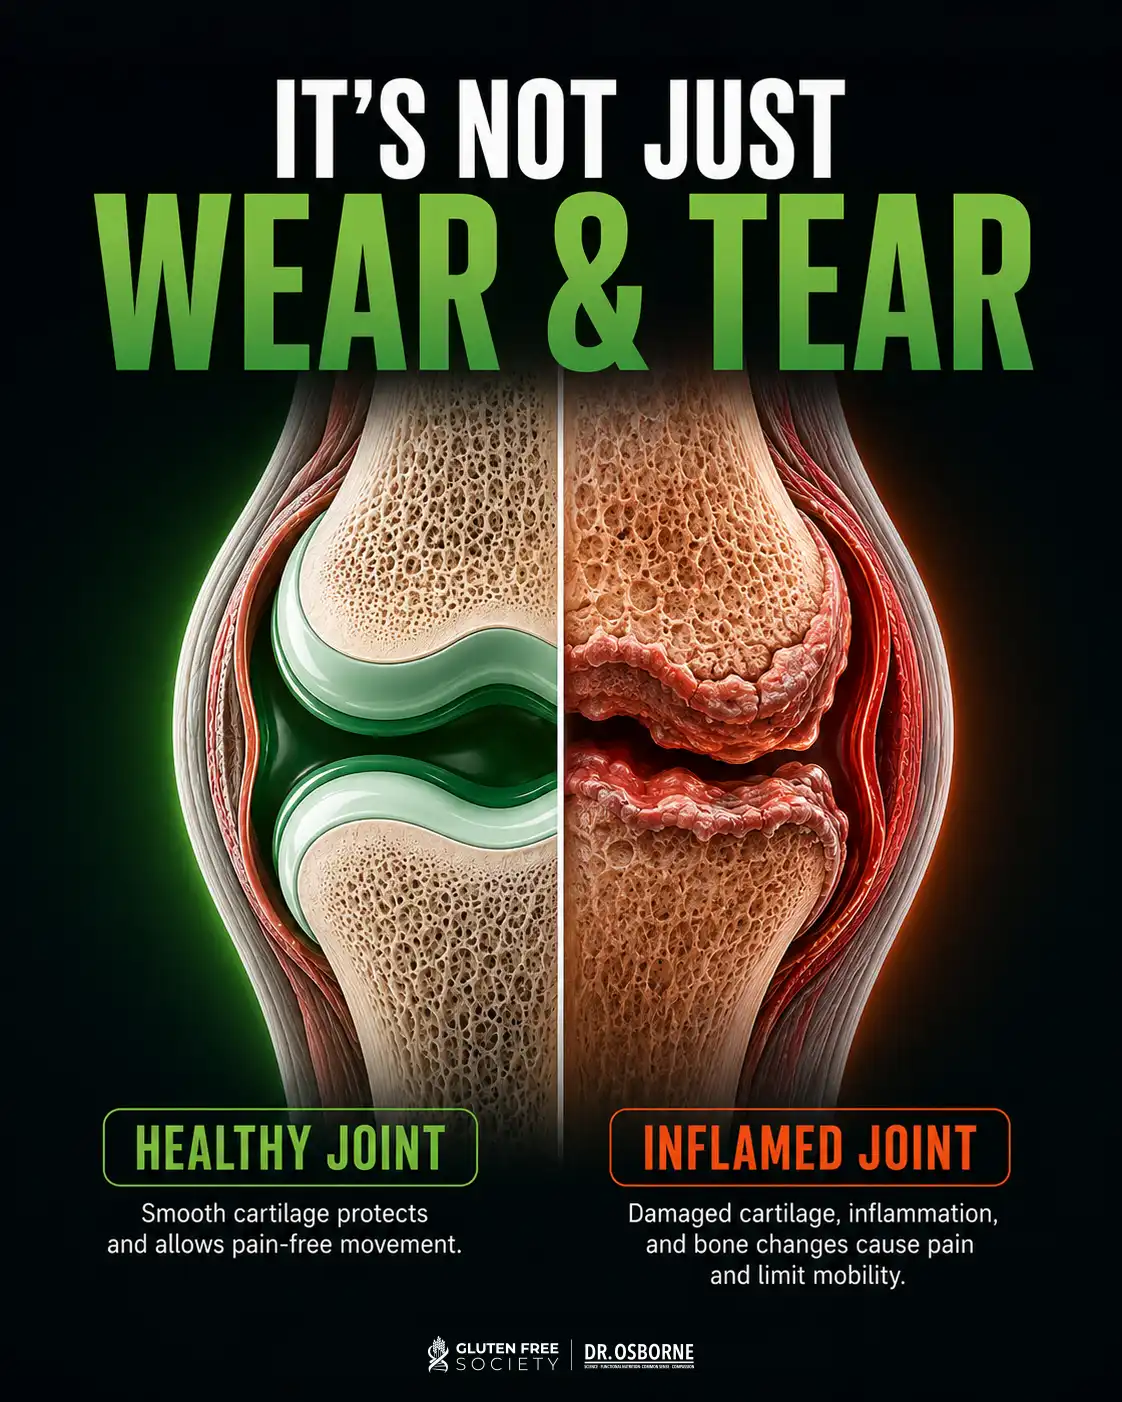
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
Type II collagen
Aggrecan
Proteoglycans
Other components of the extracellular matrix
These cells must maintain a constant balance between tissue breakdown and tissue rebuilding. Vitamin C supports several aspects of this process because it participates in collagen synthesis and protects cells against oxidative stress. This creates an important nutritional principle: Cartilage cannot maintain itself efficiently without the nutrients required for cartilage production.
Pain relief is important, but joint nutrition should also address what cartilage actually needs to function.
Vitamin C From Food
Unlike most animals, humans cannot manufacture vitamin C internally.
We must obtain it through food or supplementation.
Good food sources include:
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
Chondrocytes
Collagen
Proteoglycans
Cell membranes
Mitochondria
DNA
Vitamin C is a water-soluble antioxidant capable of donating electrons to reactive molecules and helping neutralize oxidative stress. It also interacts with other antioxidant systems in the body. This is especially relevant because oxidative stress and inflammation can reinforce one another. Free radicals can amplify inflammatory signaling, while inflammation creates more reactive oxygen species. Vitamin C therefore plays two complementary roles:
Structural
Supporting collagen formation.
Protective
Helping defend connective tissue against oxidative damage.
What the Human Research Shows
One of the few direct randomized human trials of vitamin C for osteoarthritis was conducted in 133 people with radiographically confirmed symptomatic osteoarthritis of the hip and/or knee. The vitamin C treatment also produced a statistically significant improvement in the Lequesne Functional Index, a measure of pain, walking ability, and daily function. Patients also experienced modest pain relief.
Some of the most interesting vitamin C findings come from the Framingham cohort. Researchers evaluated 640 people and compared dietary antioxidant intake with the development and progression of knee osteoarthritis. Higher vitamin C intake was strongly associated with a lower risk of osteoarthritis progression. Participants with higher vitamin C intake also had a significantly lower risk of developing knee pain. The authors concluded that higher antioxidant intake, particularly vitamin C, may reduce cartilage loss and osteoarthritis progression.
An analysis from the Osteoarthritis Initiative studied 1,785 people with knee osteoarthritis. Researchers evaluated vitamin C intake along with MRI measurements. Higher vitamin C intake was associated with healthier cartilage.
Why Vitamin C May Be Especially Important When Taking Collagen
Later in this article, collagen appears as an honorable mention supplement. There is an important biological connection between collagen supplementation and vitamin C. Collagen supplements provide amino acids and peptides that the body can use in connective-tissue metabolism. But supplying collagen peptides does not eliminate the need for the cofactors required to process and stabilize newly synthesized collagen. Vitamin C remains necessary.
Vitamin C and Chondrocytes
Chondrocytes are the cells responsible for maintaining cartilage.
They produce:
Type II collagen
Aggrecan
Proteoglycans
Other components of the extracellular matrix
These cells must maintain a constant balance between tissue breakdown and tissue rebuilding. Vitamin C supports several aspects of this process because it participates in collagen synthesis and protects cells against oxidative stress. This creates an important nutritional principle: Cartilage cannot maintain itself efficiently without the nutrients required for cartilage production.
Pain relief is important, but joint nutrition should also address what cartilage actually needs to function.
Vitamin C From Food
Unlike most animals, humans cannot manufacture vitamin C internally.
We must obtain it through food or supplementation.
Good food sources include:
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
Prolyl hydroxylase
Lysyl hydroxylase
These enzymes modify the amino acids proline and lysine during collagen synthesis. That hydroxylation process allows newly produced collagen chains to form the stable triple-helix structure characteristic of mature collagen. Without adequate vitamin C, collagen cannot be assembled and stabilized normally. This biology is not theoretical. Severe vitamin C deficiency causes scurvy, a disease characterized by defective collagen production resulting in bleeding gums, fragile blood vessels, poor wound healing, musculoskeletal pain, and connective-tissue failure.
2. Vitamin C Supports Cartilage Matrix Production
Collagen is only part of cartilage.
Healthy cartilage also contains large proteoglycan molecules that help retain water and absorb pressure. Vitamin C is essential not only in collagen formation but also in glycosaminoglycan and proteoglycan metabolism, both central components of the cartilage extracellular matrix.
This means vitamin C potentially supports both major sides of cartilage structure:
Mechanical stress, inflammation, mitochondrial dysfunction, and inflammatory cytokines can increase production of reactive oxygen species.
These molecules can damage:
Chondrocytes
Collagen
Proteoglycans
Cell membranes
Mitochondria
DNA
Vitamin C is a water-soluble antioxidant capable of donating electrons to reactive molecules and helping neutralize oxidative stress. It also interacts with other antioxidant systems in the body. This is especially relevant because oxidative stress and inflammation can reinforce one another. Free radicals can amplify inflammatory signaling, while inflammation creates more reactive oxygen species. Vitamin C therefore plays two complementary roles:
Structural
Supporting collagen formation.
Protective
Helping defend connective tissue against oxidative damage.
What the Human Research Shows
One of the few direct randomized human trials of vitamin C for osteoarthritis was conducted in 133 people with radiographically confirmed symptomatic osteoarthritis of the hip and/or knee. The vitamin C treatment also produced a statistically significant improvement in the Lequesne Functional Index, a measure of pain, walking ability, and daily function. Patients also experienced modest pain relief.
Some of the most interesting vitamin C findings come from the Framingham cohort. Researchers evaluated 640 people and compared dietary antioxidant intake with the development and progression of knee osteoarthritis. Higher vitamin C intake was strongly associated with a lower risk of osteoarthritis progression. Participants with higher vitamin C intake also had a significantly lower risk of developing knee pain. The authors concluded that higher antioxidant intake, particularly vitamin C, may reduce cartilage loss and osteoarthritis progression.
An analysis from the Osteoarthritis Initiative studied 1,785 people with knee osteoarthritis. Researchers evaluated vitamin C intake along with MRI measurements. Higher vitamin C intake was associated with healthier cartilage.
Why Vitamin C May Be Especially Important When Taking Collagen
Later in this article, collagen appears as an honorable mention supplement. There is an important biological connection between collagen supplementation and vitamin C. Collagen supplements provide amino acids and peptides that the body can use in connective-tissue metabolism. But supplying collagen peptides does not eliminate the need for the cofactors required to process and stabilize newly synthesized collagen. Vitamin C remains necessary.
Vitamin C and Chondrocytes
Chondrocytes are the cells responsible for maintaining cartilage.
They produce:
Type II collagen
Aggrecan
Proteoglycans
Other components of the extracellular matrix
These cells must maintain a constant balance between tissue breakdown and tissue rebuilding. Vitamin C supports several aspects of this process because it participates in collagen synthesis and protects cells against oxidative stress. This creates an important nutritional principle: Cartilage cannot maintain itself efficiently without the nutrients required for cartilage production.
Pain relief is important, but joint nutrition should also address what cartilage actually needs to function.
Vitamin C From Food
Unlike most animals, humans cannot manufacture vitamin C internally.
We must obtain it through food or supplementation.
Good food sources include:
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
Water
Type II collagen
Proteoglycans
Glycosaminoglycans
Specialized cartilage cells called chondrocytes
The collagen framework gives cartilage tensile strength and structural organization. Proteoglycans trap water inside that framework, allowing cartilage to absorb compression. If collagen production is impaired, the tissue itself becomes structurally weaker. Vitamin C participates directly in that process.
These enzymes modify the amino acids proline and lysine during collagen synthesis. That hydroxylation process allows newly produced collagen chains to form the stable triple-helix structure characteristic of mature collagen. Without adequate vitamin C, collagen cannot be assembled and stabilized normally. This biology is not theoretical. Severe vitamin C deficiency causes scurvy, a disease characterized by defective collagen production resulting in bleeding gums, fragile blood vessels, poor wound healing, musculoskeletal pain, and connective-tissue failure.
2. Vitamin C Supports Cartilage Matrix Production
Collagen is only part of cartilage.
Healthy cartilage also contains large proteoglycan molecules that help retain water and absorb pressure. Vitamin C is essential not only in collagen formation but also in glycosaminoglycan and proteoglycan metabolism, both central components of the cartilage extracellular matrix.
This means vitamin C potentially supports both major sides of cartilage structure:
Mechanical stress, inflammation, mitochondrial dysfunction, and inflammatory cytokines can increase production of reactive oxygen species.
These molecules can damage:
Chondrocytes
Collagen
Proteoglycans
Cell membranes
Mitochondria
DNA
Vitamin C is a water-soluble antioxidant capable of donating electrons to reactive molecules and helping neutralize oxidative stress. It also interacts with other antioxidant systems in the body. This is especially relevant because oxidative stress and inflammation can reinforce one another. Free radicals can amplify inflammatory signaling, while inflammation creates more reactive oxygen species. Vitamin C therefore plays two complementary roles:
Structural
Supporting collagen formation.
Protective
Helping defend connective tissue against oxidative damage.
What the Human Research Shows
One of the few direct randomized human trials of vitamin C for osteoarthritis was conducted in 133 people with radiographically confirmed symptomatic osteoarthritis of the hip and/or knee. The vitamin C treatment also produced a statistically significant improvement in the Lequesne Functional Index, a measure of pain, walking ability, and daily function. Patients also experienced modest pain relief.
Some of the most interesting vitamin C findings come from the Framingham cohort. Researchers evaluated 640 people and compared dietary antioxidant intake with the development and progression of knee osteoarthritis. Higher vitamin C intake was strongly associated with a lower risk of osteoarthritis progression. Participants with higher vitamin C intake also had a significantly lower risk of developing knee pain. The authors concluded that higher antioxidant intake, particularly vitamin C, may reduce cartilage loss and osteoarthritis progression.
An analysis from the Osteoarthritis Initiative studied 1,785 people with knee osteoarthritis. Researchers evaluated vitamin C intake along with MRI measurements. Higher vitamin C intake was associated with healthier cartilage.
Why Vitamin C May Be Especially Important When Taking Collagen
Later in this article, collagen appears as an honorable mention supplement. There is an important biological connection between collagen supplementation and vitamin C. Collagen supplements provide amino acids and peptides that the body can use in connective-tissue metabolism. But supplying collagen peptides does not eliminate the need for the cofactors required to process and stabilize newly synthesized collagen. Vitamin C remains necessary.
Vitamin C and Chondrocytes
Chondrocytes are the cells responsible for maintaining cartilage.
They produce:
Type II collagen
Aggrecan
Proteoglycans
Other components of the extracellular matrix
These cells must maintain a constant balance between tissue breakdown and tissue rebuilding. Vitamin C supports several aspects of this process because it participates in collagen synthesis and protects cells against oxidative stress. This creates an important nutritional principle: Cartilage cannot maintain itself efficiently without the nutrients required for cartilage production.
Pain relief is important, but joint nutrition should also address what cartilage actually needs to function.
Vitamin C From Food
Unlike most animals, humans cannot manufacture vitamin C internally.
We must obtain it through food or supplementation.
Good food sources include:
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
Reduced osteoarthritis pain with calcium ascorbate
Better functional scores
Lower risk of cartilage loss with higher vitamin C intake
Lower risk of knee OA progression in a major longitudinal cohort
Associations between higher vitamin C intake and healthier cartilage MRI characteristics
Vitamin C also plays a direct, non-negotiable role in the chemistry of collagen formation.
Why Vitamin C Is So Important for Your Joints
Cartilage is made largely from:
Water
Type II collagen
Proteoglycans
Glycosaminoglycans
Specialized cartilage cells called chondrocytes
The collagen framework gives cartilage tensile strength and structural organization. Proteoglycans trap water inside that framework, allowing cartilage to absorb compression. If collagen production is impaired, the tissue itself becomes structurally weaker. Vitamin C participates directly in that process.
These enzymes modify the amino acids proline and lysine during collagen synthesis. That hydroxylation process allows newly produced collagen chains to form the stable triple-helix structure characteristic of mature collagen. Without adequate vitamin C, collagen cannot be assembled and stabilized normally. This biology is not theoretical. Severe vitamin C deficiency causes scurvy, a disease characterized by defective collagen production resulting in bleeding gums, fragile blood vessels, poor wound healing, musculoskeletal pain, and connective-tissue failure.
2. Vitamin C Supports Cartilage Matrix Production
Collagen is only part of cartilage.
Healthy cartilage also contains large proteoglycan molecules that help retain water and absorb pressure. Vitamin C is essential not only in collagen formation but also in glycosaminoglycan and proteoglycan metabolism, both central components of the cartilage extracellular matrix.
This means vitamin C potentially supports both major sides of cartilage structure:
Mechanical stress, inflammation, mitochondrial dysfunction, and inflammatory cytokines can increase production of reactive oxygen species.
These molecules can damage:
Chondrocytes
Collagen
Proteoglycans
Cell membranes
Mitochondria
DNA
Vitamin C is a water-soluble antioxidant capable of donating electrons to reactive molecules and helping neutralize oxidative stress. It also interacts with other antioxidant systems in the body. This is especially relevant because oxidative stress and inflammation can reinforce one another. Free radicals can amplify inflammatory signaling, while inflammation creates more reactive oxygen species. Vitamin C therefore plays two complementary roles:
Structural
Supporting collagen formation.
Protective
Helping defend connective tissue against oxidative damage.
What the Human Research Shows
One of the few direct randomized human trials of vitamin C for osteoarthritis was conducted in 133 people with radiographically confirmed symptomatic osteoarthritis of the hip and/or knee. The vitamin C treatment also produced a statistically significant improvement in the Lequesne Functional Index, a measure of pain, walking ability, and daily function. Patients also experienced modest pain relief.
Some of the most interesting vitamin C findings come from the Framingham cohort. Researchers evaluated 640 people and compared dietary antioxidant intake with the development and progression of knee osteoarthritis. Higher vitamin C intake was strongly associated with a lower risk of osteoarthritis progression. Participants with higher vitamin C intake also had a significantly lower risk of developing knee pain. The authors concluded that higher antioxidant intake, particularly vitamin C, may reduce cartilage loss and osteoarthritis progression.
An analysis from the Osteoarthritis Initiative studied 1,785 people with knee osteoarthritis. Researchers evaluated vitamin C intake along with MRI measurements. Higher vitamin C intake was associated with healthier cartilage.
Why Vitamin C May Be Especially Important When Taking Collagen
Later in this article, collagen appears as an honorable mention supplement. There is an important biological connection between collagen supplementation and vitamin C. Collagen supplements provide amino acids and peptides that the body can use in connective-tissue metabolism. But supplying collagen peptides does not eliminate the need for the cofactors required to process and stabilize newly synthesized collagen. Vitamin C remains necessary.
Vitamin C and Chondrocytes
Chondrocytes are the cells responsible for maintaining cartilage.
They produce:
Type II collagen
Aggrecan
Proteoglycans
Other components of the extracellular matrix
These cells must maintain a constant balance between tissue breakdown and tissue rebuilding. Vitamin C supports several aspects of this process because it participates in collagen synthesis and protects cells against oxidative stress. This creates an important nutritional principle: Cartilage cannot maintain itself efficiently without the nutrients required for cartilage production.
Pain relief is important, but joint nutrition should also address what cartilage actually needs to function.
Vitamin C From Food
Unlike most animals, humans cannot manufacture vitamin C internally.
We must obtain it through food or supplementation.
Good food sources include:
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
The Science-Backed Natural Guide to Relieving Osteoarthritis Pain Naturally
If you have osteoarthritis, you’ve probably heard the same advice over and over: “Take a pain reliever, lose some weight, and learn to live with it.”
Unfortunately, that advice falls short for millions of people. If you are looking for a natural solution, keep reading. I will be breaking down my favorite top supplements for arthritis pain. Let’s dive in.
More than 32 million adults in the United States have osteoarthritis, making it the most common form of arthritis. It is a leading cause of chronic pain, disability, reduced mobility, and joint replacement surgery. Whether your pain affects your knees, hips, hands, shoulders, or spine, the underlying problem is much more complex than simply “wear and tear.” Osteoarthritis is now recognized as a disease involving chronic low-grade inflammation, oxidative stress, cartilage breakdown, and changes to the underlying bone and surrounding tissues. These processes work together to create pain, stiffness, swelling, and progressive loss of joint function.
Pain medications can temporarily reduce symptoms, but they do little to support the biological processes responsible for maintaining healthy joints. Nutritional strategies, targeted supplementation, regular movement, and an anti-inflammatory diet offer an opportunity to support the body’s natural repair mechanisms while helping reduce many of the processes that contribute to ongoing joint degeneration.
That is where science becomes encouraging.
Over the past two decades, researchers have conducted hundreds of human clinical trials evaluating nutritional supplements for osteoarthritis. Several have consistently demonstrated improvements in pain, stiffness, physical function, walking ability, and quality of life. While no supplement can completely reverse advanced arthritis, some have shown impressive benefits by helping calm inflammation, protect cartilage, reduce oxidative damage, and support healthier joint metabolism.
This guide reviews five of the most extensively studied supplements for osteoarthritis:
Omega-3 fatty acids
Turmeric (Curcumin)
Glucosamine and Chondroitin
Boswellia
Vitamin C
I will also cover several additional supplements that I have found to be invaluable in my clinical practice, including collagen, B vitamins, quercetin, and white willow bark, all of which have promising research behind them.
Beyond supplements, you’ll discover why diet and exercise remain two of the most powerful tools for reducing arthritis pain. We’ll explore how the No Grain No Pain approach may help lower inflammatory burden, improve metabolic health, and support healthier joints.
Every major recommendation in this article is supported by published human research so you can understand not only what works, but why it works.
By the end, you’ll have an evidence-based roadmap to help you make informed decisions about supporting healthier joints naturally.
What Is Osteoarthritis?
Osteoarthritis (OA) is the most common form of arthritis, affecting hundreds of millions of people worldwide. Although it has traditionally been described as a disease caused by “wear and tear,” researchers now understand that osteoarthritis is a biologically active condition involving inflammation, oxidative stress, abnormal tissue remodeling, and failed repair of the joint.
A healthy joint is a remarkable piece of engineering. The ends of your bones are covered with a smooth layer of cartilage that allows them to glide across one another with almost no friction. This cartilage is composed primarily of water, type II collagen, and specialized proteins called proteoglycans that act like microscopic shock absorbers. Living within this tissue are cells called chondrocytes, whose job is to continuously maintain and repair the cartilage matrix.
Surrounding the joint is a thin membrane called the synovium, which produces synovial fluid. This slippery fluid lubricates the joint, cushions impact, and delivers nutrients to cartilage. Unlike most tissues in the body, cartilage has virtually no direct blood supply. Every step you take gently compresses the cartilage, helping move nutrients in and waste products out. That means healthy movement is essential for keeping cartilage alive.
Beneath the cartilage lies subchondral bone, which provides structural support. Ligaments stabilize the joint, tendons connect muscles to bone, and surrounding muscles absorb much of the force generated during movement. When all of these structures work together, your joints move smoothly and painlessly.
Osteoarthritis develops when damage accumulates faster than the body can repair it in what I often call a repair deficit.
Small injuries accumulate faster than cartilage can recover. Chondrocytes become less effective at maintaining healthy tissue. Inflammatory chemicals increase inside the joint, oxidative stress damages cells, cartilage begins to thin, and the underlying bone responds by becoming thicker and developing bony outgrowths called osteophytes. At the same time, the synovium may become inflamed, producing inflammatory mediators that further accelerate cartilage breakdown.
The result is a vicious cycle. As cartilage deteriorates, the joint becomes less stable. Reduced movement weakens surrounding muscles, increasing mechanical stress on the joint. More stress leads to more inflammation, more tissue damage, and ultimately more pain.
Understanding where osteoarthritis pain actually comes from changes the conversation about treatment. If pain is being driven by inflammation, oxidative stress, abnormal joint signaling, and progressive cartilage breakdown, not simply aging cartilage, then supporting these biological processes becomes an important part of a comprehensive strategy for maintaining healthier joints.
That is precisely where targeted nutrition and evidence-based supplementation may provide meaningful support.
Key Takeaways
Osteoarthritis is far more than “wear and tear.” It is a biologically active disease involving inflammation, oxidative stress, cartilage degeneration, and abnormal bone remodeling.
Cartilage depends on healthy movement and proper nutrition because it has virtually no direct blood supply.
Much of the pain of osteoarthritis comes from systemic inflammation as well as inflamed joint tissues and underlying bone rather than the cartilage itself.
Because multiple biological processes contribute to osteoarthritis, no single therapy addresses every aspect of the disease.
The supplements discussed in this guide work through different mechanisms, allowing them to target inflammation, cartilage health, oxidative stress, and joint function from multiple angles.
Why Supplements Can Help Osteoarthritis
Osteoarthritis is not caused by one isolated defect, so it rarely responds completely to one isolated treatment.
The joint is a living system. Cartilage, bone, synovial tissue, muscles, ligaments, tendons, immune cells, nerves, and blood vessels all influence how that joint feels and functions. As osteoarthritis progresses, inflammation increases, cartilage loses structural integrity, oxidative damage accumulates, pain nerves become more sensitive, and the muscles supporting the joint often become weaker.
This creates several different biological targets for nutritional support.
Some supplements help regulate inflammatory signaling. Others provide raw materials used to build cartilage, collagen, and joint fluid. Certain nutrients protect cells against oxidative damage, while others influence pain signaling or help the body bring an inflammatory response to a proper conclusion.
That distinction is important. Reducing pain is valuable, but a comprehensive strategy should also support the tissues and biological processes responsible for maintaining the joint.
Osteoarthritis Is an Inflammatory Condition
Osteoarthritis was once viewed primarily as mechanical deterioration caused by age and repetitive use. Mechanical stress certainly plays a role, but the modern understanding of osteoarthritis is far more complex.
These chemicals are not merely bystanders. They can increase pain sensitivity, reduce the production of healthy cartilage components, and activate enzymes that physically break down the cartilage matrix.
This is one reason targeted supplements may be useful. Omega-3 fats, curcumin, Boswellia, glucosamine, chondroitin, and vitamin C do not all work in the same way. Each interacts with different parts of the inflammatory and structural pathways involved in osteoarthritis.
NF-κB: The Inflammatory Master Switch
One of the most important inflammatory pathways involved in osteoarthritis is called nuclear factor kappa B, usually abbreviated NF-κB.
Think of NF-κB as a master switch that turns on a large collection of inflammatory genes.
When cartilage cells are exposed to injury, oxidative stress, excess mechanical pressure, or inflammatory cytokines, NF-κB can become activated. Once switched on, it signals the cell to increase the production of inflammatory mediators and cartilage-degrading enzymes.
This pathway will come up repeatedly throughout this article because several of the supplements discussed, especially curcumin and Boswellia, appear to influence signaling systems connected to NF-κB.
COX-2 and Prostaglandins: Turning Inflammation Into Pain
Inflammation and pain are closely connected through an enzyme called cyclooxygenase-2, or COX-2. COX-2 helps convert fatty acids into inflammatory compounds called prostaglandins. One of these, prostaglandin E2, makes the nerves surrounding the joint more sensitive to pain. This means the same movement or pressure that might feel normal in a healthy joint can feel painful in an inflamed joint.
Nonsteroidal anti-inflammatory drugs, including ibuprofen and naproxen, reduce pain partly by inhibiting cyclooxygenase enzymes and decreasing prostaglandin production. Some nutritional compounds influence related inflammatory pathways, although they do not necessarily act with the same potency, speed, or pharmacology as an NSAID.
Curcumin has been studied for its effects on COX-2, NF-κB, cytokines, and oxidative stress. Boswellia appears to work more strongly through another enzyme pathway involving 5-lipoxygenase. Omega-3 fats may shift the fatty-acid environment away from compounds that promote inflammation and toward compounds involved in resolving it.
These differences help explain why combining dietary strategies with carefully selected supplements may provide broader support than relying on a single pathway.
5-Lipoxygenase and Leukotrienes
Cyclooxygenase is not the only pathway that converts fats into inflammatory compounds. The enzyme 5-lipoxygenase, commonly shortened to 5-LOX, helps produce leukotrienes. Leukotrienes can promote immune-cell activity, inflammation, swelling, and tissue irritation. Boswellia is particularly interesting because boswellic acids, especially acetyl-11-keto-beta-boswellic acid, have been studied for their ability to influence the 5-LOX pathway. This gives Boswellia a mechanism that is different from many common pain-relieving compounds. Rather than simply duplicating the action of turmeric or an NSAID, it may address another branch of inflammatory chemistry. That is one reason Boswellia and curcumin are frequently combined in joint-support formulations. They overlap in some biological effects but are not identical.
Matrix Metalloproteinases: Enzymes That Break Down Cartilage
Healthy cartilage is built from an organized extracellular matrix composed primarily of:
In osteoarthritis, enzymes called matrix metalloproteinases, or MMPs, begin degrading this matrix faster than the cartilage cells can rebuild it. MMP-13 is particularly important because it can break down type II collagen. Other enzymes, including ADAMTS-4 and ADAMTS-5, degrade aggrecan.
Inflammatory signaling through IL-1β, TNF-α, NF-κB, and related pathways can increase the production of these destructive enzymes. As proteoglycans are lost, cartilage becomes less capable of resisting compression. As collagen breaks down, the structural framework begins to fail.
This process helps explain why osteoarthritis can continue progressing even after the original injury or mechanical stress has passed. Once inflammatory signals and matrix-degrading enzymes remain active, cartilage destruction can become self-perpetuating.
Glucosamine and chondroitin are often discussed in this context because they are closely related to compounds used within the cartilage matrix. Curcumin, Boswellia, and omega-3 fats may provide additional support by influencing inflammatory signals that stimulate cartilage-degrading enzymes.
Oxidative Stress Damages Cartilage Cells
Inflammation is only part of the story.
The joint also produces unstable molecules called reactive oxygen species, commonly referred to as free radicals. In healthy amounts, these molecules participate in normal cellular signaling. When their production overwhelms the body’s antioxidant defenses, oxidative stress develops.
Oxidative stress can damage:
Chondrocyte membranes
Cellular proteins
Mitochondria
DNA
Type II collagen
Proteoglycans
The enzymes required for tissue maintenance
Oxidative stress can also activate NF-κB, increasing inflammatory signaling and creating a feedback loop of inflammation driving pain – pain driving reduced movement – reduced movement leading to muscle weakness – muscle weakness causing joint instability – instability causing mechanical stress – stress causing inflammation. Cartilage lacks a blood supply, and depends on joint movement to receive nutrients to maintain its health and integrity. When pain leads to movement avoidance, the joint is destined for progressive arthritis and eventually failure that may require surgical intervention.
Research has connected this interaction between oxidative stress and NF-κB signaling with cartilage remodeling, synovial inflammation, chondrocyte death, and osteoarthritis progression. Vitamin C becomes especially important here. It acts as an antioxidant, but its role goes beyond neutralizing free radicals. Vitamin C is also required for the enzymes that stabilize newly formed collagen. That means inadequate vitamin C can create two problems simultaneously: weaker antioxidant protection and impaired collagen production.
Chondrocytes Need Nutritional Support
Chondrocytes are the cells responsible for maintaining cartilage. They produce collagen, proteoglycans, aggrecan, and other components of the extracellular matrix.
In a healthy joint, chondrocytes balance two opposing activities:
Anabolism: building and repairing cartilage
Catabolism: breaking down old or damaged tissue
Osteoarthritis shifts that balance toward catabolism. Inflammatory cytokines tell chondrocytes to reduce cartilage production and increase destructive enzymes. Oxidative stress damages their mitochondria. Mechanical overload changes cellular signaling. As the disease progresses, some chondrocytes become dysfunctional, enter cellular senescence, or die.
The extracellular matrix surrounding these cells also changes. Because chondrocytes respond to their physical environment, a damaged matrix can send abnormal signals back to the cells, further impairing repair. This creates another self-reinforcing cycle in which damaged cartilage promotes cellular dysfunction, and dysfunctional cells produce weaker cartilage.
Supplements cannot overcome severe mechanical instability or replace missing cartilage. They may, however, help create a more favorable nutritional and inflammatory environment in which the remaining joint tissues can function.
Supporting Collagen and Proteoglycan Production
Cartilage repair requires raw materials. Type II collagen forms a fibrous network that resists stretching and shearing forces. Proteoglycans hold water and resist compression. If the body lacks the nutrients needed to build and stabilize these compounds, tissue maintenance becomes more difficult.
Several of the supplements in this article relate directly or indirectly to cartilage structure:
Vitamin C is required for collagen hydroxylation and stabilization.
Glucosamine is used in pathways associated with glycosaminoglycan production.
Chondroitinis a structural component of cartilage proteoglycans.
Collagen peptides provide amino acids and bioactive peptides that may influence joint tissues.
Omega-3 fats, curcumin, and Boswellia may help reduce inflammatory signaling that accelerates matrix destruction.
Resolving Inflammation Is Different From Blocking It
Inflammation is not inherently harmful. It is a normal survival response designed to contain damage, remove injured cells, and begin repair. The trouble begins when inflammation does not shut off properly. The body has active resolution pathways that signal immune cells to stop escalating the inflammatory response, clear cellular debris, and transition toward tissue repair. These pathways are influenced by a family of compounds called specialized pro-resolving mediators, or SPMs.
Blocking inflammation attempts to suppress inflammatory chemistry.
Resolving inflammation helps the body complete the inflammatory process and transition toward cleanup and repair.
Omega-3 fatty acids are unique among the five featured supplements because they provide precursors for these pro-resolving compounds. This does not mean every dose of fish oil automatically produces a predictable amount of SPMs. Conversion depends on enzymes, nutrient cofactors, health status, medications, and individual biology. It does, however, provide an additional mechanism through which omega-3 fats may influence joint health.
Pain Sensitization: Why the Joint Can Keep Hurting
Osteoarthritis pain does not always correspond perfectly with the degree of cartilage loss visible on an X-ray. Inflammatory chemicals can sensitize pain receptors around the joint. Repeated pain signaling can make local nerves more reactive, causing normal movement, pressure, or temperature changes to produce stronger pain signals. Over time, persistent pain may also alter the way the spinal cord and brain process incoming signals. This is sometimes called central sensitization.
At the same time, pain discourages movement. Reduced movement weakens the muscles surrounding the joint. Weak muscles provide less stability and absorb less force, placing more pressure on the damaged joint. Supplements may help reduce some of the inflammatory inputs contributing to pain sensitivity, but they cannot substitute for progressive movement and muscle strengthening.
Different Supplements Target Different Problems (My Top 5 Supplements for Arthritis Pain)
The value of these five supplements is not that they all do the same thing. Their value lies in their differences.
Collagen production, antioxidant defense and connective-tissue support
This is why asking, “Which supplement is best?” may be less useful than identifying the processes contributing most heavily to the individual’s pain. One person may have significant metabolic inflammation and oxidative stress. Another may have a history of joint trauma and poor mechanical stability. A third may have nutrient insufficiency, weak connective tissue, low muscle mass, or a diet dominated by sugar and refined carbohydrates. The supplement should be matched to the biology whenever possible.
Supplements Work Best When the Joint Environment Changes
A supplement cannot fully compensate for:
The body cannot repair effectively while the signals driving damage remain in place. This is why the most successful osteoarthritis strategy combines four priorities:
Reduce the inflammatory burden.
Supply the nutrients required for joint maintenance.
Restore movement, strength, and mechanical stability.
Remove dietary and lifestyle factors that repeatedly promote damage
NF-κB acts as a major inflammatory switch that increases cytokines and cartilage-degrading enzymes.
COX-2, prostaglandins, 5-LOX, and leukotrienes contribute to inflammation and joint pain through different pathways.
MMPs and aggrecanases break down type II collagen and proteoglycans within cartilage.
Oxidative stress damages cartilage cells and can further activate inflammatory signaling.
Vitamin C, glucosamine, and chondroitin support structural aspects of connective tissue and cartilage metabolism.
Omega-3 fats provide precursors used to produce specialized pro-resolving mediators.
Supplements work best when paired with an anti-inflammatory diet, appropriate exercise, muscle strengthening, sleep, and weight management.
No single supplement addresses every biological driver of osteoarthritis.
Supplement #1 for Arthritis Pain: Omega-3 Fatty Acids
The Best Studied Fat for Calming Inflammation and Supporting Joint Health
If there were one nutrient that almost every person with osteoarthritis should evaluate, omega-3 fatty acids would be on the top of the list. Unlike many supplements that work through a single pathway, omega-3s influence numerous biological processes involved in osteoarthritis. They help regulate inflammatory signaling, reduce the production of inflammatory compounds, support healthier cell membranes, protect cartilage from excessive breakdown, and provide the raw materials your body uses to produce specialized molecules that help bring inflammation to a healthy conclusion. For these reasons, omega-3 fatty acids have become one of the most extensively studied nutritional interventions for chronic inflammatory conditions, including osteoarthritis.
What Are Omega-3 Fatty Acids?
Omega-3 fatty acids are essential fats required for normal body functioning. The body cannot produce them. They must come from the diet or supplementation.
The three primary omega-3 fats are:
ALA (alpha-linolenic acid) – found in flaxseed, chia seeds, walnuts, and hemp.
EPA (eicosapentaenoic acid) – found primarily in cold-water fish and fish oil.
DHA (docosahexaenoic acid) – also found in marine foods and fish oil.
Although plant foods contain ALA, humans convert only a small percentage into EPA and DHA. Most studies demonstrating benefits for osteoarthritis have used EPA- and DHA-rich marine omega-3 supplements rather than plant-based ALA.
How Omega-3s Work
Omega-3s don’t simply “reduce inflammation.” They help reshape the inflammatory environment inside the joint through several complementary mechanisms.
1. They Reduce the Production of Inflammatory Chemicals Called Eicosanoids
Many inflammatory compounds are made from omega-6 fatty acids, particularly arachidonic acid. When arachidonic acid is converted by COX and LOX enzymes, it produces prostaglandins and leukotrienes that contribute to pain, swelling, and inflammation.
EPA competes with arachidonic acid for these same enzymes. As EPA intake increases, the body produces fewer highly inflammatory eicosanoids and more compounds that are substantially less inflammatory. Rather than acting like a drug that shuts inflammation off, omega-3s help shift the body’s inflammatory chemistry toward a more balanced state.
These compounds are produced from EPA and DHA. Their job is different from traditional anti-inflammatory medications.
Instead of simply blocking inflammation, SPMs help the body complete the inflammatory response by:
stopping excessive immune cell recruitment
clearing damaged tissue
promoting debris removal
encouraging tissue repair
helping restore normal tissue function
Think of inflammation like a construction crew repairing a damaged bridge. Traditional anti-inflammatory drugs slow the workers down. SPMs help the workers finish the job, clean up the construction site, and reopen the bridge. This concept is particularly important in osteoarthritis because unresolved inflammation contributes to continued cartilage degeneration.
These inflammatory pathways stimulate matrix metalloproteinases (MMPs), enzymes that gradually digest cartilage. By reducing these inflammatory signals, omega-3s may help slow the excessive breakdown of cartilage that characterizes osteoarthritis.
Every cell in your joints is surrounded by a membrane made largely of fat. The types of fats incorporated into these membranes influence how cells communicate and respond to inflammation. Increasing EPA and DHA changes membrane composition, making inflammatory signaling less aggressive while improving membrane fluidity and cellular communication.
6. Omega-3s Enhance Blood Flow
The microvasculature that feeds the subchondral bone and adjacent joint structures is responsible for delivering oxygen and nutrients while aiding in the removal of cellular waste products. Studies show that omega-3 improves vascular elasticity and blood flow.
How Much Should You Take?
Most successful clinical trials have used between 1,000 and 3,000 mg per day of combined EPA and DHA, although the optimal dose varies depending on dietary intake, body size, and the degree of inflammation.
When choosing a supplement, pay closer attention to the actual EPA and DHA content than to the total amount of fish oil listed on the label. A product labeled “1,000 mg fish oil” may provide only 300–400 mg of EPA plus DHA, while a concentrated formulation can provide substantially more.
Clinically speaking, it is always better to test Omega-3 levels. In patients with very low levels, I sometimes have to administer up to 6,000 mg/day (combined EPA and DHA). Though rare, this higher dose is sometimes necessary to achieve a positive outcome. Most of the patients I have seen do well with 2,000-4,000 mg/day. A word of caution: At higher doses, some people experience a blood thinning effect. If you are taking blood thinners, work with a nutritionally knowledgeable doctor to monitor your needs.
Food Sources
Excellent dietary sources include:
Wild Salmon
Sardines
Mackerel
Anchovies
Herring
While these foods provide valuable omega-3s, many people do not consume them regularly enough to achieve the intake levels used in clinical research.
Who May Benefit Most?
Omega-3 supplementation may be particularly helpful for people who:
Have osteoarthritis
Consume little seafood
Have diets high in processed vegetable oils
Have had intestinal or gall bladder surgery leading to fat malabsorption
Have inflammatory bowel diseases causing fat malabsorption
Have chronic low-grade inflammation
Experience morning stiffness
Have multiple painful joints
What the Research Shows
Mechanisms
✓ Supports inflammation resolution
✓ Helps regulate NF-κB
✓ Influences COX and LOX pathways
✓ Supports healthier cartilage metabolism
✓ Reduces oxidative stress
✓ Supports healthier cell membranes
Clinical Outcomes Observed in Human Studies
✓ Reduced pain
✓ Reduced stiffness
✓ Improved walking ability
✓ Improved physical function
✓ Improved quality of life
✓ Improved vascular flow into the surrounding joint structures
Key Takeaways
Omega-3 fatty acids do far more than reduce inflammation. They help shift the body’s inflammatory chemistry, provide the building blocks for specialized pro-resolving mediators, protect cartilage from excessive inflammatory damage, improve blood flow, and support healthier joint function. Their broad range of biological effects, combined with positive human research studies, make them one of the strongest nutritional foundations for a comprehensive osteoarthritis support program.
Supplement #2: Turmeric and Curcumin
One of the Best-Studied Botanical Options for Osteoarthritis Pain
Turmeric has moved far beyond its traditional use as a culinary spice. Concentrated turmeric and curcumin extracts have now been tested in numerous randomized human trials involving people with osteoarthritis, particularly osteoarthritis of the knee. Across systematic reviews, curcumin supplementation has been associated with reductions in joint pain and stiffness and improvements in physical function. Several trials have also found symptom relief comparable to commonly used anti-inflammatory medications, including ibuprofen and diclofenac, with fewer gastrointestinal complaints reported in some studies.
Turmeric and Curcumin Are Not the Same Thing
Turmeric is the yellow-orange rhizome of the plant Curcuma longa. The whole root contains curcuminoids, volatile oils, carbohydrates, proteins, minerals, and numerous other naturally occurring plant compounds.
Curcumin is the most extensively studied curcuminoid found within turmeric. It is primarily responsible for turmeric’s yellow pigment and is one of the compounds most closely associated with turmeric’s anti-inflammatory and antioxidant effects.
Most positive osteoarthritis trials have not used ordinary culinary turmeric alone. They have used one of the following:
Standardized turmeric extracts
Concentrated curcuminoids
Bioavailability-enhanced curcumin
Water-dispersible curcumin
Phospholipid or phytosome preparations
Curcumin combined with turmeric essential oils
This distinction is critical. A teaspoon of turmeric added to food may not be equivalent to the concentrated or enhanced-absorption formulations used in clinical research.
How Curcumin May Reduce Osteoarthritis Pain
Curcumin does not appear to work through one isolated pathway. Experimental and human research indicates that it can influence several biological processes involved in pain, inflammatory signaling, oxidative stress, and cartilage metabolism.
1. Curcumin Influences NF-κB Signaling
NF-κB acts as an inflammatory control switch inside the cell. When it becomes activated, it increases the expression of genes involved in cytokine production, cyclooxygenase activity, nitric oxide production, and enzymes capable of degrading joint tissue.
Curcumin has been shown in mechanistic research to influence NF-κB and several downstream inflammatory signals. This provides a plausible explanation for the reductions in pain and stiffness observed in human osteoarthritis trials. However, the clinically established outcome is symptom improvement. Claims that curcumin permanently switches off inflammation or reverses joint damage would exceed the available human evidence.
2. Curcumin May Reduce Inflammatory Cytokine Activity
Osteoarthritic joints can produce increased amounts of inflammatory signaling compounds, including:
Interleukin-1 beta
Tumor necrosis factor alpha
Interleukin-6
Prostaglandin E2
Nitric oxide
These compounds can increase pain sensitivity and stimulate enzymes involved in cartilage-matrix breakdown.
Curcumin has demonstrated the ability to influence several of these pathways in experimental models. In a human knee-osteoarthritis trial comparing a bioavailable turmeric extract with paracetamol, the turmeric group experienced reductions in inflammatory biomarkers including C-reactive protein and tumor necrosis factor alpha alongside symptom improvement.
3. Curcumin May Influence COX and Prostaglandin Signaling
Cyclooxygenase enzymes participate in the production of prostaglandins, compounds that contribute to inflammation and pain sensitivity.
NSAIDs such as ibuprofen and diclofenac reduce pain partly by interfering with cyclooxygenase activity. Curcumin is not a natural version of an NSAID and does not have identical pharmacology, but it can influence cyclooxygenase-related inflammatory pathways along with several additional signaling systems. The clinical relevance of this broader activity is supported by trials in which turmeric or curcumin extracts produced symptom improvement comparable to ibuprofen or diclofenac.
4. Curcumin Helps Regulate Oxidative Stress
Inflamed and mechanically stressed joint tissues generate reactive oxygen species. When antioxidant defenses cannot keep pace, oxidative stress can damage cell membranes, mitochondria, proteins, and components of the cartilage matrix.
Curcumin can act directly as an antioxidant and may also influence the body’s internal antioxidant systems. In a randomized, double-blind, placebo-controlled trial involving people with knee osteoarthritis, curcuminoid supplementation improved several measures of systemic oxidative stress. Researchers believe that turmeric’s antioxidant properties may be one major reason why it helps those with OA pain.
5. Curcumin May Influence Cartilage-Degrading Enzymes
Inflammatory cytokines can increase the activity of matrix metalloproteinases and aggrecanases, enzymes involved in breaking down collagen and proteoglycans within cartilage. Laboratory research suggests curcumin can influence these catabolic signals. Supporting these findings, a one-year placebo-controlled human study of curcumin reported favorable changes in MRI-based cartilage measurements.
What the Human Research Shows
Systematic Review and Meta-Analysis of Randomized Trials
Significant reductions in joint pain compared with placebo
Symptom outcomes that were comparable to conventional pain medications
Good tolerability without the kidney and GI concerns that come with NSAIDs.
The authors concluded that the available randomized trials supported the use of turmeric extracts providing approximately 1,000 milligrams of curcumin per day for arthritis symptoms.
Review of Turmeric for Knee-Osteoarthritis Pain and Function
The authors found stronger results in studies lasting longer than 12 weeks, although duration should still be considered alongside formulation, dose, and baseline symptom severity.
Curcumin Compared With Ibuprofen
Four-Week Multicenter Trial
A randomized multicenter trial included 367 adults with primary knee osteoarthritis and clinically significant knee pain.
Participants received either:
1,500 milligrams of Curcuma domestica extract daily
1,200 milligrams of ibuprofen daily
Treatment continued for four weeks, and both groups improved significantly in:
Pain reduction
Stiffness
Physical function
The turmeric extract met the study’s criteria for noninferiority to ibuprofen (Turmeric was equally effective as ibuprofen). Patients taking turmeric had less GI side effects than those taking ibuprofen.
The researchers found similar improvements in pain and function between the treatments and concluded that the turmeric extract appeared similarly effective and safe.
After 28 days, both groups experienced significant improvements in knee-osteoarthritis symptoms. Curcumin produced symptom relief similar to diclofenac and caused fewer adverse effects.
Adverse events were reported by:
13% of the curcumin group
38% of the diclofenac group
The curcumin group also experienced fewer gastrointestinal complaints and no participants withdrew because of adverse effects.
Compared with placebo, curcumin significantly improved:
Knee-pain scores
Numerical knee-pain ratings
Additional Research Studies on Curcumin and Osteoarthritis Improvements
An eight-week study evaluated a water-dispersible curcumin preparation in people with knee osteoarthritis. The researchers reported improvements in several clinical symptoms, particularly among participants with more severe baseline pain.
A multicenter, double-blind, randomized, placebo-controlled study evaluated two doses of Curcuma longa extract in people with symptomatic knee osteoarthritis. The extract improved knee pain compared with placebo, and the study found a reduction in rescue-medication use.
A 90-day randomized, double-blind, placebo-controlled trial evaluated a solid-lipid curcumin formulation in adults with knee osteoarthritis. The curcumin group experienced significant improvements in pain, stiffness, and physical function compared with placebo.
How Much Curcumin Was Used in Human Studies?
Verified osteoarthritis trials have used doses ranging from 300 to 3,000 mg daily. Trial times have ranged from 4 weeks to one year. In my clinical experience, 1,000-3,000 mg daily doses have been most effective for osteoarthritis pain patients. Some people respond to lower doses while others may require more. There is no one size fits all approach to curcumin use.
How Long Does Curcumin Take to Work?
In my clinic, I typically see results in as little as a few days, but for some it may take up to 4 weeks. Some comparative trials reported meaningful symptom improvement within four weeks. Placebo-controlled studies commonly lasted eight to 12 weeks, and several systematic reviews found stronger or more consistent results with longer treatment periods.
A reasonable evaluation period is generally four to 12 weeks, depending on the formulation and the severity of symptoms. Curcumin is not an anesthetic. It does not numb the joint immediately. Its benefits appear to develop as inflammatory signaling, oxidative balance, and pain sensitivity change over time. And in my experience, it works even better when paired with vitamin C, quercetin, Omega-3, and diet change (No Grain No Pain).
Who May Benefit Most?
Curcumin may be particularly useful for people who:
Have symptomatic knee, hand, shoulder, back, hip, and ankle osteoarthritis
Experience persistent pain and stiffness
Want an evidence-based botanical option
Have difficulty tolerating frequent NSAID use
Need support for both inflammatory and oxidative pathways
Are combining supplementation with exercise, strength training, and dietary changes
Turmeric and Curcumin Research Summary
Evidence category
What verified human research supports
Knee pain
Improved in multiple randomized trials and meta-analyses
Joint stiffness
Improved in several trials and pooled analyses
Physical function
Improved in multiple randomized trials and systematic reviews
Comparison with ibuprofen
Similar short-term symptom improvement in direct-comparison trials
Comparison with diclofenac
Similar symptom improvement with fewer reported adverse effects in one open-label trial
Gastrointestinal tolerability
Favorable in several comparative trials
Inflammatory biomarkers
Improved in selected formulation-specific studies
Oxidative-stress markers
Improved in a randomized human trial
Cartilage preservation
Preliminary studies show improvements
Cartilage regeneration
Not established
Universal effective dose
Not established
Most studied joint
Knee
Key Turmeric/Curcumin Takeaways
Turmeric and curcumin are among the most thoroughly studied botanical supplements for knee osteoarthritis. Systematic reviews consistently report improvements in pain and physical function compared with placebo. Direct-comparison trials have found symptom relief similar to ibuprofen and diclofenac, with fewer gastrointestinal adverse effects reported. The strongest research evidence supports standardized extracts and bioavailability-enhanced formulations, not ordinary turmeric powder. Dose recommendations must be tied to the formulation because curcumin absorption varies dramatically among products.
Curcumin should be viewed as a multi-pathway tool for reducing osteoarthritis symptoms. It influences inflammatory signaling, oxidative stress, prostaglandin-related pathways, and pain sensitivity. Human evidence supports improvements in pain, stiffness, and function. My clinical experience has shown curcumin to be a powerful alternative to help people reduce pain and improve their functionality and quality of life without the nutrient-depleting effects, gastrointestinal, and kidney complications associated with NSAID use.
Supplement #3: Glucosamine and Chondroitin
Structural Joint Nutrients With Human Evidence for Pain, Function, and Cartilage Support
Glucosamine and chondroitin are two of the most recognizable supplements used for osteoarthritis. They are often sold together, but they are not identical compounds, and they do not necessarily produce identical effects.
Glucosamine is an amino sugar involved in pathways used to produce glycosaminoglycans, proteoglycans, and other components of connective tissue. Chondroitin sulfate is a sulfated glycosaminoglycan naturally present within cartilage, where it helps the tissue attract water and resist compression.
That basic biology explains why these nutrients have attracted so much attention. Osteoarthritis gradually damages the collagen-and-proteoglycan matrix that allows cartilage to absorb force. Glucosamine and chondroitin provide compounds related to that matrix while also influencing inflammatory and cartilage-degrading pathways.
Human research has reported benefits in several important areas:
Reduced osteoarthritis pain
Less stiffness
Improved physical function
Improved mobility
Reduced joint swelling in some trials
Slower radiographic joint-space loss in selected long-term studies
What Is Glucosamine?
Glucosamine is a naturally occurring amino sugar that the body uses in biochemical pathways associated with connective tissue. It is involved in the production of compounds found in:
Cartilage
Tendons
Ligaments
Synovial fluid
Proteoglycans
Glycosaminoglycans
Positive clinical trials have most commonly used 1500 milligrams of glucosamine sulfate daily.
What Is Chondroitin Sulfate?
Chondroitin sulfate is a long-chain sulfated molecule found naturally within cartilage and other connective tissues. Within cartilage, chondroitin is incorporated into large proteoglycan structures. These molecules attract and hold water, helping cartilage resist compression and rebound after force is applied. Cartilage is not a dry cushion. It is a highly hydrated tissue. Its water-binding capacity is central to its ability to distribute pressure across the joint.
Chondroitin sulfate has also been studied for effects on:
Pain
Physical function
Morning stiffness
Joint swelling
Cartilage metabolism
Joint-space narrowing
Positive clinical trials have most commonly used 800 to 1,200 milligrams of chondroitin sulfate daily.
How Glucosamine and Chondroitin May Help Osteoarthritis
1. They Support the Proteoglycan-Rich Cartilage Matrix
Healthy cartilage is built around a network of type II collagen, proteoglycans, glycosaminoglycans, and water. Type II collagen provides tensile strength. Proteoglycans attract water and give cartilage its ability to withstand compression. Glucosamine participates in pathways used to produce glycosaminoglycans. Chondroitin sulfate is itself a glycosaminoglycan component of cartilage proteoglycans.
2. They May Help Regulate Cartilage Breakdown
Osteoarthritis shifts cartilage metabolism toward destruction. Inflammatory cytokines can activate enzymes including matrix metalloproteinases and aggrecanases. These enzymes break down collagen and aggrecan faster than cartilage cells can replace them. Experimental research suggests that glucosamine and chondroitin may influence inflammatory signaling and reduce the activity of some cartilage-degrading enzymes. The most clinically meaningful support for this mechanism comes from long-term human studies reporting less joint-space loss in groups receiving glucosamine sulfate or chondroitin sulfate.
3. They May Improve Joint Hydration and Shock Absorption
Chondroitin-containing proteoglycans attract water into the cartilage matrix. This water-binding capacity helps cartilage:
Distribute pressure
Absorb impact
Maintain elasticity
Rebound after compression
Protect the bone beneath the joint surface
A loss of proteoglycans causes cartilage to become less resilient. Chondroitin supplementation is intended to support the matrix components involved in this process.
4. They May Reduce Inflammatory Signaling
Glucosamine and chondroitin are not simply inert building blocks. Laboratory evidence indicates that they may influence:
NF-κB signaling
Prostaglandin production
Cytokine activity
Nitric oxide production
Matrix metalloproteinases
Aggrecan-degrading enzymes
These actions may help explain why clinical trials have found improvements in pain, stiffness, function, and swelling rather than only structural outcomes.
5. They Work Slowly
Glucosamine and chondroitin are generally categorized as slow-acting agents. They do not work like aspirin, ibuprofen, or an anesthetic. Their effects tend to develop gradually as joint metabolism, inflammatory signaling, and tissue turnover change. Most meaningful clinical trials have lasted from 3 months and as long as several years.
What the Human Research Shows for Glucosamine Sulfate
After three years, the placebo group had lost an average of 0.31 millimeters of joint-space width, while the glucosamine-sulfate group had no statistically significant mean joint-space loss, with a change of 0.06 millimeters. Symptoms measured by the WOMAC osteoarthritis index also worsened slightly in the placebo group while improving in the glucosamine group. This trial is especially important because it evaluated more than short-term pain. It examined symptoms and radiographic joint structure over three years.
The six-month GUIDE trial evaluated1,500 mg of prescription glucosamine sulfate once daily in adults with knee osteoarthritis. Glucosamine sulfate produced a significantly greater improvement in pain, function, and disability.
Aside from the above research, many other studies have shown positive pain benefits for patients taking 1500 mg of glucosamine daily.
What the Human Research Shows for Chondroitin Sulfate
A Cochrane review evaluated randomized trials of chondroitin used alone or with glucosamine. Compared with placebo, chondroitin produced improvements in pain and functionality.
Another study called The CONCEPT trial, was a six-month, randomized, double-blind study involving 604 adults with symptomatic knee osteoarthritis. The study compared chondroitin to the prescription pain drug, Celecoxib, and a placebo. Chondroitin sulfate was superior to placebo for reducing pain and improving physical function. Its effects were comparable to celecoxib.
A one-year, randomized, double-blind pilot study included 42 adults with symptomatic knee osteoarthritis. 800 mg of chondroitin significantly reduced joint pain and improved mobility. The study also showed that chondroitin preserved the joint space of the knee.
A multicenter, randomized, double-blind, placebo-controlled study evaluated intermittent chondroitin-sulfate treatment for one year in people with knee osteoarthritis. The trial reported symptomatic benefits and supported the use of chondroitin as a slow-acting osteoarthritis intervention.
This was the dose used in major long-term knee-osteoarthritis trials and across most studies included in the glucosamine-sulfate umbrella review.
Chondroitin Sulfate
Positive studies commonly used:
800 to 1,200 mg daily
How Long Does It Take to Work?
Glucosamine and chondroitin should be evaluated as slow-acting joint-support compounds.
Positive studies reported benefits over:
Four months
Six months
One year
Three years
The MOVES trial demonstrated that the combination gradually reached outcomes comparable to celecoxib by six months. The long-term glucosamine-sulfate trial evaluated joint-space width and symptoms over three years.
A practical trial should generally last at least three to six months, provided the product, dose, and formulation resemble those used in positive research.
Stopping after one or two weeks does not meaningfully test a slow-acting cartilage-support strategy.
Who May Benefit Most?
Glucosamine and chondroitin may be especially useful for people who:
Have mild-to-moderate knee osteoarthritis
Experience chronic pain and stiffness rather than an acute injury
Want support for cartilage metabolism in addition to pain relief
Prefer a slow-acting nutritional strategy
Are willing to use a studied dose consistently
Are early enough in the disease process to retain meaningful cartilage
Want to combine structural support with exercise and an anti-inflammatory diet
Have hand osteoarthritis, particularly when considering chondroitin sulfate
The strongest direct research concerns knee osteoarthritis, with additional positive evidence for chondroitin in hand osteoarthritis.
When Glucosamine and Chondroitin Make the Most Sense
These supplements make the most biological sense when they are used as part of a strategy that reduces ongoing joint damage.
That includes:
Improving muscle strength around the joint
Correcting movement mechanics
Reducing excess body weight when appropriate
Stabilizing blood sugar
Removing inflammatory foods
Eating adequate protein
Correcting vitamin C and other nutrient insufficiencies
Avoiding repetitive mechanical overload
Maintaining regular low-impact movement
Supplying cartilage-related nutrients while continuing to expose the joint to poor mechanics, sugar overload, inactivity, and chronic inflammation limits what any supplement can accomplish.
Glucosamine and Chondroitin Research Summary
Evidence category
What positive human research supports
Knee pain
Improved in multiple trials and evidence reviews
Stiffness
Improved in glucosamine-chondroitin combination trials
Physical function
Improved with glucosamine sulfate, chondroitin sulfate, and selected combinations
Comparison with celecoxib
Combination and pharmaceutical-grade chondroitin produced comparable outcomes in major trials
Hand osteoarthritis
Chondroitin improved pain, function, grip strength, and morning stiffness
Joint swelling
Improved in the MOVES combination trial
Joint-space narrowing
Slower loss reported in selected long-term glucosamine- and chondroitin-sulfate trials
Cartilage regeneration
Not established
Most studied glucosamine form
Crystalline glucosamine sulfate
Common glucosamine dose
1,500 mg daily
Common chondroitin dose
800–1,200 mg daily
Expected timeline
Usually several months
Product-quality importance
High
Key Takeaways
Glucosamine and chondroitin are different compounds that support overlapping aspects of joint biology.
Glucosamine is involved in pathways used to produce glycosaminoglycans and proteoglycans. Chondroitin sulfate is a structural component of cartilage that helps the tissue attract water and resist compression.
Positive human trials support benefits for:
Pain
Stiffness
Mobility
Physical function
Joint swelling
Hand function
Long-term joint-space preservation in selected studies
The strongest glucosamine evidence centers on 1,500 mg of crystalline glucosamine sulfate daily. The strongest chondroitin studies commonly used 800 to 1,200 mg of standardized pharmaceutical-grade chondroitin sulfate.
These nutrients are not fast painkillers. They are slow-acting compounds that should be used consistently and evaluated over three to six months or longer. Product quality determines whether the bottle in someone’s hand resembles the formulation used in research. The name “glucosamine and chondroitin” on the front label is not enough. The form, dose, purity, standardization, and manufacturing quality all influence whether the supplement has a realistic chance of reproducing clinical results.
In my clinical practice, I commonly recommend a combination formula that contains glucosamine, chondroitin, and MSM. This combination of ingredients very commonly reduces the pain and stiffness for many of my patients.
Supplement #4: Boswellia
A Fast-Acting Botanical for Osteoarthritis Pain, Stiffness, and Function
Boswellia serrata, commonly known as Indian frankincense, has been used traditionally for inflammatory conditions for centuries. Modern research has focused on concentrated extracts from the plant’s gum resin, particularly standardized preparations rich in boswellic acids.
For osteoarthritis, the human evidence is surprisingly strong.
Randomized controlled trials have reported improvements in:
Knee pain
Joint stiffness
Walking ability
Physical function
WOMAC scores
Lequesne Functional Index scores
Joint swelling in some studies
Several trials have also reported improvements within the first week of supplementation, making Boswellia one of the faster-acting supplements discussed in this article.
A 2020 systematic review and meta-analysis of seven randomized controlled trials involving 545 people with osteoarthritis found that Boswellia significantly improved pain, stiffness, and physical function.
What Is Boswellia?
Boswellia serrata is a tree native to India, North Africa, and parts of the Middle East. Its resin contains a group of pentacyclic triterpenes collectively known as boswellic acids.
The compounds that receive the most research attention include:
Boswellia extracts differ substantially in their composition and concentration of boswellic acids. Many of the positive clinical trials have evaluated standardized formulations rather than generic Boswellia powders. Some of the best-studied preparations include:
Boswellia is often described as a “natural 5-LOX inhibitor.” There is some truth to that, but the biology is more complicated than the marketing slogan. The enzyme 5-lipoxygenase, or 5-LOX, participates in the conversion of arachidonic acid into leukotrienes, inflammatory lipid mediators involved in immune signaling.
AKBA has demonstrated direct interactions with 5-LOX in laboratory studies. Early research showed that AKBA could influence 5-LOX activity through an allosteric mechanism rather than by competing directly with arachidonic acid at the enzyme’s active site. (Review the mechanistic research)
More recent structural research has confirmed that AKBA binds to an allosteric region of 5-LOX and can alter the enzyme’s activity and the pattern of lipid products it generates. (Review the structural research)
However, pharmacokinetic research has raised an important point: circulating concentrations of AKBA after ordinary oral Boswellia supplementation may be much lower than the concentrations required to reproduce some laboratory effects. Other boswellic acids, including β-boswellic acid, reach higher circulating concentrations and may influence additional inflammatory enzymes. (Read the pharmacology review)
Bottom line: Boswellia contains multiple boswellic acids that influence several inflammatory pathways, including 5-LOX-related signaling, prostaglandin pathways, proteolytic enzymes, and inflammatory cellular responses.
2. Boswellia May Reduce Cartilage-Degrading Enzymes
Osteoarthritis involves increased activity of enzymes capable of degrading the cartilage matrix. One of these is matrix metalloproteinase-3, or MMP-3. MMP-3 can participate in breakdown of:
Proteoglycans
Fibronectin
Other extracellular-matrix proteins
A 90-day randomized trial evaluating 5-Loxin measured MMP-3 directly in the synovial fluid of people with knee osteoarthritis. The higher-dose Boswellia group showed a significant reduction in synovial-fluid MMP-3, providing human evidence that this extract may influence a biological pathway associated with cartilage degradation.
3. Boswellia May Reduce Systemic Inflammatory Markers
A more recent randomized, double-blind, placebo-controlled trial evaluated an enhanced-bioavailability Boswellia extract called Aflapin in people with knee osteoarthritis. After 30 days, the Boswellia group showed reductions in several circulating markers associated with inflammation and cartilage turnover, including:
TNF-α
High-sensitivity CRP
MMP-3
C2C, a marker of type II collagen breakdown
At the same time, participants experienced significant improvements in pain, stiffness, and function.
4. Boswellia Can Improve Pain Without Acting Like a Conventional NSAID
NSAIDs primarily work by interfering with cyclooxygenase enzymes and prostaglandin production. Boswellia interacts with a broader and somewhat different network of inflammatory pathways. This makes Boswellia particularly interesting as part of a multi-target strategy. Turmeric, omega-3 fats, Boswellia, glucosamine, chondroitin, and vitamin C do not simply duplicate one another.
Boswellia appears especially useful for targeting:
Inflammatory lipid signaling
Joint pain
Stiffness
MMP activity
Physical function
Synovial inflammatory activity
What the Human Research Shows
A 2020 systematic review and meta-analysis evaluated seven randomized controlled trials involving 545 osteoarthritis patients. Compared with placebo or conventional treatment, Boswellia significantly improved pain, stiffness, and joint function. The authors concluded that Boswellia extracts may be effective and safe for osteoarthritis and found that improvements generally became apparent after at least four weeks of treatment.
One of the earliest controlled human trials evaluated Boswellia serrata extract in 30 people with knee osteoarthritis using a randomized, double-blind, placebo-controlled crossover design. Participants received Boswellia extract or placebo for eight weeks before crossing over to the alternate treatment. During Boswellia treatment, participants experienced reduced knee pain, increased range of motion, improved walking distance, and reduced knee swelling.
A 2008 randomized, double-blind, placebo-controlled trial evaluated 75 adults with knee osteoarthritis. The patients reported improvements in both pain and physical function. Patients receiving 250 mg doses experienced relief is as little as seven days. Boswellia also led to reduced inflammation markers in the synovial fluid of patients taking it.
A 2023 randomized, double-blind, placebo-controlled trial involving 70 adults with knee osteoarthritis who were given 100 mg of boswellia extract (aflapin) daily for 30 days. The outcomes were impressive. Patients reported less pain, stuffness, improved joint function, and follow up labs showed reductions in inflammatory markers.
Taken together, the available human data support a consistent pattern. Boswellia extracts can reduce osteoarthritis pain, improve stiffness, and improve physical function.
How Much Boswellia Was Used in Positive Human Studies?
Human trial doses varied between 100 mg/day and 250 mg/day.
How Fast Can Boswellia Work?
Research studies show pain relief in less than a week of use. In my experience, relief can happen much more quickly for some. Especially at higher doses and when mixed with white willow. Many patients report pain relief within hours of use.
Key Takeaways
Boswellia has some of the most compelling human evidence among botanical supplements for osteoarthritis. It is one of the fastest working natural compounds when it comes to pain relief.
Supplement #5: Vitamin C
An Essential Nutrient for Collagen Production, Cartilage Integrity, and Antioxidant Defense
Vitamin C is rarely marketed as an arthritis supplement, but from a biological standpoint, it is one of the most important nutrients for connective tissue. Your body cannot make collagen properly without it. Important because collagen is one of the primary structural proteins in cartilage, tendons, ligaments, bone, and other tissues that stabilize and protect joints. Vitamin C is also a major antioxidant that helps protect cartilage cells from oxidative stress.
For osteoarthritis, the human evidence is not as extensive as the evidence for curcumin or Boswellia. There are fewer randomized controlled trials specifically testing vitamin C as a treatment for OA pain. But the available human data are positive and biologically compelling.
Human studies have reported:
Reduced osteoarthritis pain with calcium ascorbate
Better functional scores
Lower risk of cartilage loss with higher vitamin C intake
Lower risk of knee OA progression in a major longitudinal cohort
Associations between higher vitamin C intake and healthier cartilage MRI characteristics
Vitamin C also plays a direct, non-negotiable role in the chemistry of collagen formation.
Why Vitamin C Is So Important for Your Joints
Cartilage is made largely from:
Water
Type II collagen
Proteoglycans
Glycosaminoglycans
Specialized cartilage cells called chondrocytes
The collagen framework gives cartilage tensile strength and structural organization. Proteoglycans trap water inside that framework, allowing cartilage to absorb compression. If collagen production is impaired, the tissue itself becomes structurally weaker. Vitamin C participates directly in that process.
These enzymes modify the amino acids proline and lysine during collagen synthesis. That hydroxylation process allows newly produced collagen chains to form the stable triple-helix structure characteristic of mature collagen. Without adequate vitamin C, collagen cannot be assembled and stabilized normally. This biology is not theoretical. Severe vitamin C deficiency causes scurvy, a disease characterized by defective collagen production resulting in bleeding gums, fragile blood vessels, poor wound healing, musculoskeletal pain, and connective-tissue failure.
2. Vitamin C Supports Cartilage Matrix Production
Collagen is only part of cartilage.
Healthy cartilage also contains large proteoglycan molecules that help retain water and absorb pressure. Vitamin C is essential not only in collagen formation but also in glycosaminoglycan and proteoglycan metabolism, both central components of the cartilage extracellular matrix.
This means vitamin C potentially supports both major sides of cartilage structure:
Mechanical stress, inflammation, mitochondrial dysfunction, and inflammatory cytokines can increase production of reactive oxygen species.
These molecules can damage:
Chondrocytes
Collagen
Proteoglycans
Cell membranes
Mitochondria
DNA
Vitamin C is a water-soluble antioxidant capable of donating electrons to reactive molecules and helping neutralize oxidative stress. It also interacts with other antioxidant systems in the body. This is especially relevant because oxidative stress and inflammation can reinforce one another. Free radicals can amplify inflammatory signaling, while inflammation creates more reactive oxygen species. Vitamin C therefore plays two complementary roles:
Structural
Supporting collagen formation.
Protective
Helping defend connective tissue against oxidative damage.
What the Human Research Shows
One of the few direct randomized human trials of vitamin C for osteoarthritis was conducted in 133 people with radiographically confirmed symptomatic osteoarthritis of the hip and/or knee. The vitamin C treatment also produced a statistically significant improvement in the Lequesne Functional Index, a measure of pain, walking ability, and daily function. Patients also experienced modest pain relief.
Some of the most interesting vitamin C findings come from the Framingham cohort. Researchers evaluated 640 people and compared dietary antioxidant intake with the development and progression of knee osteoarthritis. Higher vitamin C intake was strongly associated with a lower risk of osteoarthritis progression. Participants with higher vitamin C intake also had a significantly lower risk of developing knee pain. The authors concluded that higher antioxidant intake, particularly vitamin C, may reduce cartilage loss and osteoarthritis progression.
An analysis from the Osteoarthritis Initiative studied 1,785 people with knee osteoarthritis. Researchers evaluated vitamin C intake along with MRI measurements. Higher vitamin C intake was associated with healthier cartilage.
Why Vitamin C May Be Especially Important When Taking Collagen
Later in this article, collagen appears as an honorable mention supplement. There is an important biological connection between collagen supplementation and vitamin C. Collagen supplements provide amino acids and peptides that the body can use in connective-tissue metabolism. But supplying collagen peptides does not eliminate the need for the cofactors required to process and stabilize newly synthesized collagen. Vitamin C remains necessary.
Vitamin C and Chondrocytes
Chondrocytes are the cells responsible for maintaining cartilage.
They produce:
Type II collagen
Aggrecan
Proteoglycans
Other components of the extracellular matrix
These cells must maintain a constant balance between tissue breakdown and tissue rebuilding. Vitamin C supports several aspects of this process because it participates in collagen synthesis and protects cells against oxidative stress. This creates an important nutritional principle: Cartilage cannot maintain itself efficiently without the nutrients required for cartilage production.
Pain relief is important, but joint nutrition should also address what cartilage actually needs to function.
Vitamin C From Food
Unlike most animals, humans cannot manufacture vitamin C internally.
We must obtain it through food or supplementation.
Good food sources include:
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.
The Science-Backed Natural Guide to Relieving Osteoarthritis Pain Naturally
If you have osteoarthritis, you’ve probably heard the same advice over and over: “Take a pain reliever, lose some weight, and learn to live with it.”
Unfortunately, that advice falls short for millions of people. If you are looking for a natural solution, keep reading. I will be breaking down my favorite top supplements for arthritis pain. Let’s dive in.
More than 32 million adults in the United States have osteoarthritis, making it the most common form of arthritis. It is a leading cause of chronic pain, disability, reduced mobility, and joint replacement surgery. Whether your pain affects your knees, hips, hands, shoulders, or spine, the underlying problem is much more complex than simply “wear and tear.” Osteoarthritis is now recognized as a disease involving chronic low-grade inflammation, oxidative stress, cartilage breakdown, and changes to the underlying bone and surrounding tissues. These processes work together to create pain, stiffness, swelling, and progressive loss of joint function.
Pain medications can temporarily reduce symptoms, but they do little to support the biological processes responsible for maintaining healthy joints. Nutritional strategies, targeted supplementation, regular movement, and an anti-inflammatory diet offer an opportunity to support the body’s natural repair mechanisms while helping reduce many of the processes that contribute to ongoing joint degeneration.
That is where science becomes encouraging.
Over the past two decades, researchers have conducted hundreds of human clinical trials evaluating nutritional supplements for osteoarthritis. Several have consistently demonstrated improvements in pain, stiffness, physical function, walking ability, and quality of life. While no supplement can completely reverse advanced arthritis, some have shown impressive benefits by helping calm inflammation, protect cartilage, reduce oxidative damage, and support healthier joint metabolism.
This guide reviews five of the most extensively studied supplements for osteoarthritis:
Omega-3 fatty acids
Turmeric (Curcumin)
Glucosamine and Chondroitin
Boswellia
Vitamin C
I will also cover several additional supplements that I have found to be invaluable in my clinical practice, including collagen, B vitamins, quercetin, and white willow bark, all of which have promising research behind them.
Beyond supplements, you’ll discover why diet and exercise remain two of the most powerful tools for reducing arthritis pain. We’ll explore how the No Grain No Pain approach may help lower inflammatory burden, improve metabolic health, and support healthier joints.
Every major recommendation in this article is supported by published human research so you can understand not only what works, but why it works.
By the end, you’ll have an evidence-based roadmap to help you make informed decisions about supporting healthier joints naturally.
What Is Osteoarthritis?
Osteoarthritis (OA) is the most common form of arthritis, affecting hundreds of millions of people worldwide. Although it has traditionally been described as a disease caused by “wear and tear,” researchers now understand that osteoarthritis is a biologically active condition involving inflammation, oxidative stress, abnormal tissue remodeling, and failed repair of the joint.
A healthy joint is a remarkable piece of engineering. The ends of your bones are covered with a smooth layer of cartilage that allows them to glide across one another with almost no friction. This cartilage is composed primarily of water, type II collagen, and specialized proteins called proteoglycans that act like microscopic shock absorbers. Living within this tissue are cells called chondrocytes, whose job is to continuously maintain and repair the cartilage matrix.
Surrounding the joint is a thin membrane called the synovium, which produces synovial fluid. This slippery fluid lubricates the joint, cushions impact, and delivers nutrients to cartilage. Unlike most tissues in the body, cartilage has virtually no direct blood supply. Every step you take gently compresses the cartilage, helping move nutrients in and waste products out. That means healthy movement is essential for keeping cartilage alive.
Beneath the cartilage lies subchondral bone, which provides structural support. Ligaments stabilize the joint, tendons connect muscles to bone, and surrounding muscles absorb much of the force generated during movement. When all of these structures work together, your joints move smoothly and painlessly.
Osteoarthritis develops when damage accumulates faster than the body can repair it in what I often call a repair deficit.
Small injuries accumulate faster than cartilage can recover. Chondrocytes become less effective at maintaining healthy tissue. Inflammatory chemicals increase inside the joint, oxidative stress damages cells, cartilage begins to thin, and the underlying bone responds by becoming thicker and developing bony outgrowths called osteophytes. At the same time, the synovium may become inflamed, producing inflammatory mediators that further accelerate cartilage breakdown.
The result is a vicious cycle. As cartilage deteriorates, the joint becomes less stable. Reduced movement weakens surrounding muscles, increasing mechanical stress on the joint. More stress leads to more inflammation, more tissue damage, and ultimately more pain.
Understanding where osteoarthritis pain actually comes from changes the conversation about treatment. If pain is being driven by inflammation, oxidative stress, abnormal joint signaling, and progressive cartilage breakdown, not simply aging cartilage, then supporting these biological processes becomes an important part of a comprehensive strategy for maintaining healthier joints.
That is precisely where targeted nutrition and evidence-based supplementation may provide meaningful support.
Key Takeaways
Osteoarthritis is far more than “wear and tear.” It is a biologically active disease involving inflammation, oxidative stress, cartilage degeneration, and abnormal bone remodeling.
Cartilage depends on healthy movement and proper nutrition because it has virtually no direct blood supply.
Much of the pain of osteoarthritis comes from systemic inflammation as well as inflamed joint tissues and underlying bone rather than the cartilage itself.
Because multiple biological processes contribute to osteoarthritis, no single therapy addresses every aspect of the disease.
The supplements discussed in this guide work through different mechanisms, allowing them to target inflammation, cartilage health, oxidative stress, and joint function from multiple angles.
Why Supplements Can Help Osteoarthritis
Osteoarthritis is not caused by one isolated defect, so it rarely responds completely to one isolated treatment.
The joint is a living system. Cartilage, bone, synovial tissue, muscles, ligaments, tendons, immune cells, nerves, and blood vessels all influence how that joint feels and functions. As osteoarthritis progresses, inflammation increases, cartilage loses structural integrity, oxidative damage accumulates, pain nerves become more sensitive, and the muscles supporting the joint often become weaker.
This creates several different biological targets for nutritional support.
Some supplements help regulate inflammatory signaling. Others provide raw materials used to build cartilage, collagen, and joint fluid. Certain nutrients protect cells against oxidative damage, while others influence pain signaling or help the body bring an inflammatory response to a proper conclusion.
That distinction is important. Reducing pain is valuable, but a comprehensive strategy should also support the tissues and biological processes responsible for maintaining the joint.
Osteoarthritis Is an Inflammatory Condition
Osteoarthritis was once viewed primarily as mechanical deterioration caused by age and repetitive use. Mechanical stress certainly plays a role, but the modern understanding of osteoarthritis is far more complex.
These chemicals are not merely bystanders. They can increase pain sensitivity, reduce the production of healthy cartilage components, and activate enzymes that physically break down the cartilage matrix.
This is one reason targeted supplements may be useful. Omega-3 fats, curcumin, Boswellia, glucosamine, chondroitin, and vitamin C do not all work in the same way. Each interacts with different parts of the inflammatory and structural pathways involved in osteoarthritis.
NF-κB: The Inflammatory Master Switch
One of the most important inflammatory pathways involved in osteoarthritis is called nuclear factor kappa B, usually abbreviated NF-κB.
Think of NF-κB as a master switch that turns on a large collection of inflammatory genes.
When cartilage cells are exposed to injury, oxidative stress, excess mechanical pressure, or inflammatory cytokines, NF-κB can become activated. Once switched on, it signals the cell to increase the production of inflammatory mediators and cartilage-degrading enzymes.
This pathway will come up repeatedly throughout this article because several of the supplements discussed, especially curcumin and Boswellia, appear to influence signaling systems connected to NF-κB.
COX-2 and Prostaglandins: Turning Inflammation Into Pain
Inflammation and pain are closely connected through an enzyme called cyclooxygenase-2, or COX-2. COX-2 helps convert fatty acids into inflammatory compounds called prostaglandins. One of these, prostaglandin E2, makes the nerves surrounding the joint more sensitive to pain. This means the same movement or pressure that might feel normal in a healthy joint can feel painful in an inflamed joint.
Nonsteroidal anti-inflammatory drugs, including ibuprofen and naproxen, reduce pain partly by inhibiting cyclooxygenase enzymes and decreasing prostaglandin production. Some nutritional compounds influence related inflammatory pathways, although they do not necessarily act with the same potency, speed, or pharmacology as an NSAID.
Curcumin has been studied for its effects on COX-2, NF-κB, cytokines, and oxidative stress. Boswellia appears to work more strongly through another enzyme pathway involving 5-lipoxygenase. Omega-3 fats may shift the fatty-acid environment away from compounds that promote inflammation and toward compounds involved in resolving it.
These differences help explain why combining dietary strategies with carefully selected supplements may provide broader support than relying on a single pathway.
5-Lipoxygenase and Leukotrienes
Cyclooxygenase is not the only pathway that converts fats into inflammatory compounds. The enzyme 5-lipoxygenase, commonly shortened to 5-LOX, helps produce leukotrienes. Leukotrienes can promote immune-cell activity, inflammation, swelling, and tissue irritation. Boswellia is particularly interesting because boswellic acids, especially acetyl-11-keto-beta-boswellic acid, have been studied for their ability to influence the 5-LOX pathway. This gives Boswellia a mechanism that is different from many common pain-relieving compounds. Rather than simply duplicating the action of turmeric or an NSAID, it may address another branch of inflammatory chemistry. That is one reason Boswellia and curcumin are frequently combined in joint-support formulations. They overlap in some biological effects but are not identical.
Matrix Metalloproteinases: Enzymes That Break Down Cartilage
Healthy cartilage is built from an organized extracellular matrix composed primarily of:
In osteoarthritis, enzymes called matrix metalloproteinases, or MMPs, begin degrading this matrix faster than the cartilage cells can rebuild it. MMP-13 is particularly important because it can break down type II collagen. Other enzymes, including ADAMTS-4 and ADAMTS-5, degrade aggrecan.
Inflammatory signaling through IL-1β, TNF-α, NF-κB, and related pathways can increase the production of these destructive enzymes. As proteoglycans are lost, cartilage becomes less capable of resisting compression. As collagen breaks down, the structural framework begins to fail.
This process helps explain why osteoarthritis can continue progressing even after the original injury or mechanical stress has passed. Once inflammatory signals and matrix-degrading enzymes remain active, cartilage destruction can become self-perpetuating.
Glucosamine and chondroitin are often discussed in this context because they are closely related to compounds used within the cartilage matrix. Curcumin, Boswellia, and omega-3 fats may provide additional support by influencing inflammatory signals that stimulate cartilage-degrading enzymes.
Oxidative Stress Damages Cartilage Cells
Inflammation is only part of the story.
The joint also produces unstable molecules called reactive oxygen species, commonly referred to as free radicals. In healthy amounts, these molecules participate in normal cellular signaling. When their production overwhelms the body’s antioxidant defenses, oxidative stress develops.
Oxidative stress can damage:
Chondrocyte membranes
Cellular proteins
Mitochondria
DNA
Type II collagen
Proteoglycans
The enzymes required for tissue maintenance
Oxidative stress can also activate NF-κB, increasing inflammatory signaling and creating a feedback loop of inflammation driving pain – pain driving reduced movement – reduced movement leading to muscle weakness – muscle weakness causing joint instability – instability causing mechanical stress – stress causing inflammation. Cartilage lacks a blood supply, and depends on joint movement to receive nutrients to maintain its health and integrity. When pain leads to movement avoidance, the joint is destined for progressive arthritis and eventually failure that may require surgical intervention.
Research has connected this interaction between oxidative stress and NF-κB signaling with cartilage remodeling, synovial inflammation, chondrocyte death, and osteoarthritis progression. Vitamin C becomes especially important here. It acts as an antioxidant, but its role goes beyond neutralizing free radicals. Vitamin C is also required for the enzymes that stabilize newly formed collagen. That means inadequate vitamin C can create two problems simultaneously: weaker antioxidant protection and impaired collagen production.
Chondrocytes Need Nutritional Support
Chondrocytes are the cells responsible for maintaining cartilage. They produce collagen, proteoglycans, aggrecan, and other components of the extracellular matrix.
In a healthy joint, chondrocytes balance two opposing activities:
Anabolism: building and repairing cartilage
Catabolism: breaking down old or damaged tissue
Osteoarthritis shifts that balance toward catabolism. Inflammatory cytokines tell chondrocytes to reduce cartilage production and increase destructive enzymes. Oxidative stress damages their mitochondria. Mechanical overload changes cellular signaling. As the disease progresses, some chondrocytes become dysfunctional, enter cellular senescence, or die.
The extracellular matrix surrounding these cells also changes. Because chondrocytes respond to their physical environment, a damaged matrix can send abnormal signals back to the cells, further impairing repair. This creates another self-reinforcing cycle in which damaged cartilage promotes cellular dysfunction, and dysfunctional cells produce weaker cartilage.
Supplements cannot overcome severe mechanical instability or replace missing cartilage. They may, however, help create a more favorable nutritional and inflammatory environment in which the remaining joint tissues can function.
Supporting Collagen and Proteoglycan Production
Cartilage repair requires raw materials. Type II collagen forms a fibrous network that resists stretching and shearing forces. Proteoglycans hold water and resist compression. If the body lacks the nutrients needed to build and stabilize these compounds, tissue maintenance becomes more difficult.
Several of the supplements in this article relate directly or indirectly to cartilage structure:
Vitamin C is required for collagen hydroxylation and stabilization.
Glucosamine is used in pathways associated with glycosaminoglycan production.
Chondroitinis a structural component of cartilage proteoglycans.
Collagen peptides provide amino acids and bioactive peptides that may influence joint tissues.
Omega-3 fats, curcumin, and Boswellia may help reduce inflammatory signaling that accelerates matrix destruction.
Resolving Inflammation Is Different From Blocking It
Inflammation is not inherently harmful. It is a normal survival response designed to contain damage, remove injured cells, and begin repair. The trouble begins when inflammation does not shut off properly. The body has active resolution pathways that signal immune cells to stop escalating the inflammatory response, clear cellular debris, and transition toward tissue repair. These pathways are influenced by a family of compounds called specialized pro-resolving mediators, or SPMs.
Blocking inflammation attempts to suppress inflammatory chemistry.
Resolving inflammation helps the body complete the inflammatory process and transition toward cleanup and repair.
Omega-3 fatty acids are unique among the five featured supplements because they provide precursors for these pro-resolving compounds. This does not mean every dose of fish oil automatically produces a predictable amount of SPMs. Conversion depends on enzymes, nutrient cofactors, health status, medications, and individual biology. It does, however, provide an additional mechanism through which omega-3 fats may influence joint health.
Pain Sensitization: Why the Joint Can Keep Hurting
Osteoarthritis pain does not always correspond perfectly with the degree of cartilage loss visible on an X-ray. Inflammatory chemicals can sensitize pain receptors around the joint. Repeated pain signaling can make local nerves more reactive, causing normal movement, pressure, or temperature changes to produce stronger pain signals. Over time, persistent pain may also alter the way the spinal cord and brain process incoming signals. This is sometimes called central sensitization.
At the same time, pain discourages movement. Reduced movement weakens the muscles surrounding the joint. Weak muscles provide less stability and absorb less force, placing more pressure on the damaged joint. Supplements may help reduce some of the inflammatory inputs contributing to pain sensitivity, but they cannot substitute for progressive movement and muscle strengthening.
Different Supplements Target Different Problems (My Top 5 Supplements for Arthritis Pain)
The value of these five supplements is not that they all do the same thing. Their value lies in their differences.
Collagen production, antioxidant defense and connective-tissue support
This is why asking, “Which supplement is best?” may be less useful than identifying the processes contributing most heavily to the individual’s pain. One person may have significant metabolic inflammation and oxidative stress. Another may have a history of joint trauma and poor mechanical stability. A third may have nutrient insufficiency, weak connective tissue, low muscle mass, or a diet dominated by sugar and refined carbohydrates. The supplement should be matched to the biology whenever possible.
Supplements Work Best When the Joint Environment Changes
A supplement cannot fully compensate for:
The body cannot repair effectively while the signals driving damage remain in place. This is why the most successful osteoarthritis strategy combines four priorities:
Reduce the inflammatory burden.
Supply the nutrients required for joint maintenance.
Restore movement, strength, and mechanical stability.
Remove dietary and lifestyle factors that repeatedly promote damage
NF-κB acts as a major inflammatory switch that increases cytokines and cartilage-degrading enzymes.
COX-2, prostaglandins, 5-LOX, and leukotrienes contribute to inflammation and joint pain through different pathways.
MMPs and aggrecanases break down type II collagen and proteoglycans within cartilage.
Oxidative stress damages cartilage cells and can further activate inflammatory signaling.
Vitamin C, glucosamine, and chondroitin support structural aspects of connective tissue and cartilage metabolism.
Omega-3 fats provide precursors used to produce specialized pro-resolving mediators.
Supplements work best when paired with an anti-inflammatory diet, appropriate exercise, muscle strengthening, sleep, and weight management.
No single supplement addresses every biological driver of osteoarthritis.
Supplement #1 for Arthritis Pain: Omega-3 Fatty Acids
The Best Studied Fat for Calming Inflammation and Supporting Joint Health
If there were one nutrient that almost every person with osteoarthritis should evaluate, omega-3 fatty acids would be on the top of the list. Unlike many supplements that work through a single pathway, omega-3s influence numerous biological processes involved in osteoarthritis. They help regulate inflammatory signaling, reduce the production of inflammatory compounds, support healthier cell membranes, protect cartilage from excessive breakdown, and provide the raw materials your body uses to produce specialized molecules that help bring inflammation to a healthy conclusion. For these reasons, omega-3 fatty acids have become one of the most extensively studied nutritional interventions for chronic inflammatory conditions, including osteoarthritis.
What Are Omega-3 Fatty Acids?
Omega-3 fatty acids are essential fats required for normal body functioning. The body cannot produce them. They must come from the diet or supplementation.
The three primary omega-3 fats are:
ALA (alpha-linolenic acid) – found in flaxseed, chia seeds, walnuts, and hemp.
EPA (eicosapentaenoic acid) – found primarily in cold-water fish and fish oil.
DHA (docosahexaenoic acid) – also found in marine foods and fish oil.
Although plant foods contain ALA, humans convert only a small percentage into EPA and DHA. Most studies demonstrating benefits for osteoarthritis have used EPA- and DHA-rich marine omega-3 supplements rather than plant-based ALA.
How Omega-3s Work
Omega-3s don’t simply “reduce inflammation.” They help reshape the inflammatory environment inside the joint through several complementary mechanisms.
1. They Reduce the Production of Inflammatory Chemicals Called Eicosanoids
Many inflammatory compounds are made from omega-6 fatty acids, particularly arachidonic acid. When arachidonic acid is converted by COX and LOX enzymes, it produces prostaglandins and leukotrienes that contribute to pain, swelling, and inflammation.
EPA competes with arachidonic acid for these same enzymes. As EPA intake increases, the body produces fewer highly inflammatory eicosanoids and more compounds that are substantially less inflammatory. Rather than acting like a drug that shuts inflammation off, omega-3s help shift the body’s inflammatory chemistry toward a more balanced state.
These compounds are produced from EPA and DHA. Their job is different from traditional anti-inflammatory medications.
Instead of simply blocking inflammation, SPMs help the body complete the inflammatory response by:
stopping excessive immune cell recruitment
clearing damaged tissue
promoting debris removal
encouraging tissue repair
helping restore normal tissue function
Think of inflammation like a construction crew repairing a damaged bridge. Traditional anti-inflammatory drugs slow the workers down. SPMs help the workers finish the job, clean up the construction site, and reopen the bridge. This concept is particularly important in osteoarthritis because unresolved inflammation contributes to continued cartilage degeneration.
These inflammatory pathways stimulate matrix metalloproteinases (MMPs), enzymes that gradually digest cartilage. By reducing these inflammatory signals, omega-3s may help slow the excessive breakdown of cartilage that characterizes osteoarthritis.
Every cell in your joints is surrounded by a membrane made largely of fat. The types of fats incorporated into these membranes influence how cells communicate and respond to inflammation. Increasing EPA and DHA changes membrane composition, making inflammatory signaling less aggressive while improving membrane fluidity and cellular communication.
6. Omega-3s Enhance Blood Flow
The microvasculature that feeds the subchondral bone and adjacent joint structures is responsible for delivering oxygen and nutrients while aiding in the removal of cellular waste products. Studies show that omega-3 improves vascular elasticity and blood flow.
How Much Should You Take?
Most successful clinical trials have used between 1,000 and 3,000 mg per day of combined EPA and DHA, although the optimal dose varies depending on dietary intake, body size, and the degree of inflammation.
When choosing a supplement, pay closer attention to the actual EPA and DHA content than to the total amount of fish oil listed on the label. A product labeled “1,000 mg fish oil” may provide only 300–400 mg of EPA plus DHA, while a concentrated formulation can provide substantially more.
Clinically speaking, it is always better to test Omega-3 levels. In patients with very low levels, I sometimes have to administer up to 6,000 mg/day (combined EPA and DHA). Though rare, this higher dose is sometimes necessary to achieve a positive outcome. Most of the patients I have seen do well with 2,000-4,000 mg/day. A word of caution: At higher doses, some people experience a blood thinning effect. If you are taking blood thinners, work with a nutritionally knowledgeable doctor to monitor your needs.
Food Sources
Excellent dietary sources include:
Wild Salmon
Sardines
Mackerel
Anchovies
Herring
While these foods provide valuable omega-3s, many people do not consume them regularly enough to achieve the intake levels used in clinical research.
Who May Benefit Most?
Omega-3 supplementation may be particularly helpful for people who:
Have osteoarthritis
Consume little seafood
Have diets high in processed vegetable oils
Have had intestinal or gall bladder surgery leading to fat malabsorption
Have inflammatory bowel diseases causing fat malabsorption
Have chronic low-grade inflammation
Experience morning stiffness
Have multiple painful joints
What the Research Shows
Mechanisms
✓ Supports inflammation resolution
✓ Helps regulate NF-κB
✓ Influences COX and LOX pathways
✓ Supports healthier cartilage metabolism
✓ Reduces oxidative stress
✓ Supports healthier cell membranes
Clinical Outcomes Observed in Human Studies
✓ Reduced pain
✓ Reduced stiffness
✓ Improved walking ability
✓ Improved physical function
✓ Improved quality of life
✓ Improved vascular flow into the surrounding joint structures
Key Takeaways
Omega-3 fatty acids do far more than reduce inflammation. They help shift the body’s inflammatory chemistry, provide the building blocks for specialized pro-resolving mediators, protect cartilage from excessive inflammatory damage, improve blood flow, and support healthier joint function. Their broad range of biological effects, combined with positive human research studies, make them one of the strongest nutritional foundations for a comprehensive osteoarthritis support program.
Supplement #2: Turmeric and Curcumin
One of the Best-Studied Botanical Options for Osteoarthritis Pain
Turmeric has moved far beyond its traditional use as a culinary spice. Concentrated turmeric and curcumin extracts have now been tested in numerous randomized human trials involving people with osteoarthritis, particularly osteoarthritis of the knee. Across systematic reviews, curcumin supplementation has been associated with reductions in joint pain and stiffness and improvements in physical function. Several trials have also found symptom relief comparable to commonly used anti-inflammatory medications, including ibuprofen and diclofenac, with fewer gastrointestinal complaints reported in some studies.
Turmeric and Curcumin Are Not the Same Thing
Turmeric is the yellow-orange rhizome of the plant Curcuma longa. The whole root contains curcuminoids, volatile oils, carbohydrates, proteins, minerals, and numerous other naturally occurring plant compounds.
Curcumin is the most extensively studied curcuminoid found within turmeric. It is primarily responsible for turmeric’s yellow pigment and is one of the compounds most closely associated with turmeric’s anti-inflammatory and antioxidant effects.
Most positive osteoarthritis trials have not used ordinary culinary turmeric alone. They have used one of the following:
Standardized turmeric extracts
Concentrated curcuminoids
Bioavailability-enhanced curcumin
Water-dispersible curcumin
Phospholipid or phytosome preparations
Curcumin combined with turmeric essential oils
This distinction is critical. A teaspoon of turmeric added to food may not be equivalent to the concentrated or enhanced-absorption formulations used in clinical research.
How Curcumin May Reduce Osteoarthritis Pain
Curcumin does not appear to work through one isolated pathway. Experimental and human research indicates that it can influence several biological processes involved in pain, inflammatory signaling, oxidative stress, and cartilage metabolism.
1. Curcumin Influences NF-κB Signaling
NF-κB acts as an inflammatory control switch inside the cell. When it becomes activated, it increases the expression of genes involved in cytokine production, cyclooxygenase activity, nitric oxide production, and enzymes capable of degrading joint tissue.
Curcumin has been shown in mechanistic research to influence NF-κB and several downstream inflammatory signals. This provides a plausible explanation for the reductions in pain and stiffness observed in human osteoarthritis trials. However, the clinically established outcome is symptom improvement. Claims that curcumin permanently switches off inflammation or reverses joint damage would exceed the available human evidence.
2. Curcumin May Reduce Inflammatory Cytokine Activity
Osteoarthritic joints can produce increased amounts of inflammatory signaling compounds, including:
Interleukin-1 beta
Tumor necrosis factor alpha
Interleukin-6
Prostaglandin E2
Nitric oxide
These compounds can increase pain sensitivity and stimulate enzymes involved in cartilage-matrix breakdown.
Curcumin has demonstrated the ability to influence several of these pathways in experimental models. In a human knee-osteoarthritis trial comparing a bioavailable turmeric extract with paracetamol, the turmeric group experienced reductions in inflammatory biomarkers including C-reactive protein and tumor necrosis factor alpha alongside symptom improvement.
3. Curcumin May Influence COX and Prostaglandin Signaling
Cyclooxygenase enzymes participate in the production of prostaglandins, compounds that contribute to inflammation and pain sensitivity.
NSAIDs such as ibuprofen and diclofenac reduce pain partly by interfering with cyclooxygenase activity. Curcumin is not a natural version of an NSAID and does not have identical pharmacology, but it can influence cyclooxygenase-related inflammatory pathways along with several additional signaling systems. The clinical relevance of this broader activity is supported by trials in which turmeric or curcumin extracts produced symptom improvement comparable to ibuprofen or diclofenac.
4. Curcumin Helps Regulate Oxidative Stress
Inflamed and mechanically stressed joint tissues generate reactive oxygen species. When antioxidant defenses cannot keep pace, oxidative stress can damage cell membranes, mitochondria, proteins, and components of the cartilage matrix.
Curcumin can act directly as an antioxidant and may also influence the body’s internal antioxidant systems. In a randomized, double-blind, placebo-controlled trial involving people with knee osteoarthritis, curcuminoid supplementation improved several measures of systemic oxidative stress. Researchers believe that turmeric’s antioxidant properties may be one major reason why it helps those with OA pain.
5. Curcumin May Influence Cartilage-Degrading Enzymes
Inflammatory cytokines can increase the activity of matrix metalloproteinases and aggrecanases, enzymes involved in breaking down collagen and proteoglycans within cartilage. Laboratory research suggests curcumin can influence these catabolic signals. Supporting these findings, a one-year placebo-controlled human study of curcumin reported favorable changes in MRI-based cartilage measurements.
What the Human Research Shows
Systematic Review and Meta-Analysis of Randomized Trials
Significant reductions in joint pain compared with placebo
Symptom outcomes that were comparable to conventional pain medications
Good tolerability without the kidney and GI concerns that come with NSAIDs.
The authors concluded that the available randomized trials supported the use of turmeric extracts providing approximately 1,000 milligrams of curcumin per day for arthritis symptoms.
Review of Turmeric for Knee-Osteoarthritis Pain and Function
The authors found stronger results in studies lasting longer than 12 weeks, although duration should still be considered alongside formulation, dose, and baseline symptom severity.
Curcumin Compared With Ibuprofen
Four-Week Multicenter Trial
A randomized multicenter trial included 367 adults with primary knee osteoarthritis and clinically significant knee pain.
Participants received either:
1,500 milligrams of Curcuma domestica extract daily
1,200 milligrams of ibuprofen daily
Treatment continued for four weeks, and both groups improved significantly in:
Pain reduction
Stiffness
Physical function
The turmeric extract met the study’s criteria for noninferiority to ibuprofen (Turmeric was equally effective as ibuprofen). Patients taking turmeric had less GI side effects than those taking ibuprofen.
The researchers found similar improvements in pain and function between the treatments and concluded that the turmeric extract appeared similarly effective and safe.
After 28 days, both groups experienced significant improvements in knee-osteoarthritis symptoms. Curcumin produced symptom relief similar to diclofenac and caused fewer adverse effects.
Adverse events were reported by:
13% of the curcumin group
38% of the diclofenac group
The curcumin group also experienced fewer gastrointestinal complaints and no participants withdrew because of adverse effects.
Compared with placebo, curcumin significantly improved:
Knee-pain scores
Numerical knee-pain ratings
Additional Research Studies on Curcumin and Osteoarthritis Improvements
An eight-week study evaluated a water-dispersible curcumin preparation in people with knee osteoarthritis. The researchers reported improvements in several clinical symptoms, particularly among participants with more severe baseline pain.
A multicenter, double-blind, randomized, placebo-controlled study evaluated two doses of Curcuma longa extract in people with symptomatic knee osteoarthritis. The extract improved knee pain compared with placebo, and the study found a reduction in rescue-medication use.
A 90-day randomized, double-blind, placebo-controlled trial evaluated a solid-lipid curcumin formulation in adults with knee osteoarthritis. The curcumin group experienced significant improvements in pain, stiffness, and physical function compared with placebo.
How Much Curcumin Was Used in Human Studies?
Verified osteoarthritis trials have used doses ranging from 300 to 3,000 mg daily. Trial times have ranged from 4 weeks to one year. In my clinical experience, 1,000-3,000 mg daily doses have been most effective for osteoarthritis pain patients. Some people respond to lower doses while others may require more. There is no one size fits all approach to curcumin use.
How Long Does Curcumin Take to Work?
In my clinic, I typically see results in as little as a few days, but for some it may take up to 4 weeks. Some comparative trials reported meaningful symptom improvement within four weeks. Placebo-controlled studies commonly lasted eight to 12 weeks, and several systematic reviews found stronger or more consistent results with longer treatment periods.
A reasonable evaluation period is generally four to 12 weeks, depending on the formulation and the severity of symptoms. Curcumin is not an anesthetic. It does not numb the joint immediately. Its benefits appear to develop as inflammatory signaling, oxidative balance, and pain sensitivity change over time. And in my experience, it works even better when paired with vitamin C, quercetin, Omega-3, and diet change (No Grain No Pain).
Who May Benefit Most?
Curcumin may be particularly useful for people who:
Have symptomatic knee, hand, shoulder, back, hip, and ankle osteoarthritis
Experience persistent pain and stiffness
Want an evidence-based botanical option
Have difficulty tolerating frequent NSAID use
Need support for both inflammatory and oxidative pathways
Are combining supplementation with exercise, strength training, and dietary changes
Turmeric and Curcumin Research Summary
Evidence category
What verified human research supports
Knee pain
Improved in multiple randomized trials and meta-analyses
Joint stiffness
Improved in several trials and pooled analyses
Physical function
Improved in multiple randomized trials and systematic reviews
Comparison with ibuprofen
Similar short-term symptom improvement in direct-comparison trials
Comparison with diclofenac
Similar symptom improvement with fewer reported adverse effects in one open-label trial
Gastrointestinal tolerability
Favorable in several comparative trials
Inflammatory biomarkers
Improved in selected formulation-specific studies
Oxidative-stress markers
Improved in a randomized human trial
Cartilage preservation
Preliminary studies show improvements
Cartilage regeneration
Not established
Universal effective dose
Not established
Most studied joint
Knee
Key Turmeric/Curcumin Takeaways
Turmeric and curcumin are among the most thoroughly studied botanical supplements for knee osteoarthritis. Systematic reviews consistently report improvements in pain and physical function compared with placebo. Direct-comparison trials have found symptom relief similar to ibuprofen and diclofenac, with fewer gastrointestinal adverse effects reported. The strongest research evidence supports standardized extracts and bioavailability-enhanced formulations, not ordinary turmeric powder. Dose recommendations must be tied to the formulation because curcumin absorption varies dramatically among products.
Curcumin should be viewed as a multi-pathway tool for reducing osteoarthritis symptoms. It influences inflammatory signaling, oxidative stress, prostaglandin-related pathways, and pain sensitivity. Human evidence supports improvements in pain, stiffness, and function. My clinical experience has shown curcumin to be a powerful alternative to help people reduce pain and improve their functionality and quality of life without the nutrient-depleting effects, gastrointestinal, and kidney complications associated with NSAID use.
Supplement #3: Glucosamine and Chondroitin
Structural Joint Nutrients With Human Evidence for Pain, Function, and Cartilage Support
Glucosamine and chondroitin are two of the most recognizable supplements used for osteoarthritis. They are often sold together, but they are not identical compounds, and they do not necessarily produce identical effects.
Glucosamine is an amino sugar involved in pathways used to produce glycosaminoglycans, proteoglycans, and other components of connective tissue. Chondroitin sulfate is a sulfated glycosaminoglycan naturally present within cartilage, where it helps the tissue attract water and resist compression.
That basic biology explains why these nutrients have attracted so much attention. Osteoarthritis gradually damages the collagen-and-proteoglycan matrix that allows cartilage to absorb force. Glucosamine and chondroitin provide compounds related to that matrix while also influencing inflammatory and cartilage-degrading pathways.
Human research has reported benefits in several important areas:
Reduced osteoarthritis pain
Less stiffness
Improved physical function
Improved mobility
Reduced joint swelling in some trials
Slower radiographic joint-space loss in selected long-term studies
What Is Glucosamine?
Glucosamine is a naturally occurring amino sugar that the body uses in biochemical pathways associated with connective tissue. It is involved in the production of compounds found in:
Cartilage
Tendons
Ligaments
Synovial fluid
Proteoglycans
Glycosaminoglycans
Positive clinical trials have most commonly used 1500 milligrams of glucosamine sulfate daily.
What Is Chondroitin Sulfate?
Chondroitin sulfate is a long-chain sulfated molecule found naturally within cartilage and other connective tissues. Within cartilage, chondroitin is incorporated into large proteoglycan structures. These molecules attract and hold water, helping cartilage resist compression and rebound after force is applied. Cartilage is not a dry cushion. It is a highly hydrated tissue. Its water-binding capacity is central to its ability to distribute pressure across the joint.
Chondroitin sulfate has also been studied for effects on:
Pain
Physical function
Morning stiffness
Joint swelling
Cartilage metabolism
Joint-space narrowing
Positive clinical trials have most commonly used 800 to 1,200 milligrams of chondroitin sulfate daily.
How Glucosamine and Chondroitin May Help Osteoarthritis
1. They Support the Proteoglycan-Rich Cartilage Matrix
Healthy cartilage is built around a network of type II collagen, proteoglycans, glycosaminoglycans, and water. Type II collagen provides tensile strength. Proteoglycans attract water and give cartilage its ability to withstand compression. Glucosamine participates in pathways used to produce glycosaminoglycans. Chondroitin sulfate is itself a glycosaminoglycan component of cartilage proteoglycans.
2. They May Help Regulate Cartilage Breakdown
Osteoarthritis shifts cartilage metabolism toward destruction. Inflammatory cytokines can activate enzymes including matrix metalloproteinases and aggrecanases. These enzymes break down collagen and aggrecan faster than cartilage cells can replace them. Experimental research suggests that glucosamine and chondroitin may influence inflammatory signaling and reduce the activity of some cartilage-degrading enzymes. The most clinically meaningful support for this mechanism comes from long-term human studies reporting less joint-space loss in groups receiving glucosamine sulfate or chondroitin sulfate.
3. They May Improve Joint Hydration and Shock Absorption
Chondroitin-containing proteoglycans attract water into the cartilage matrix. This water-binding capacity helps cartilage:
Distribute pressure
Absorb impact
Maintain elasticity
Rebound after compression
Protect the bone beneath the joint surface
A loss of proteoglycans causes cartilage to become less resilient. Chondroitin supplementation is intended to support the matrix components involved in this process.
4. They May Reduce Inflammatory Signaling
Glucosamine and chondroitin are not simply inert building blocks. Laboratory evidence indicates that they may influence:
NF-κB signaling
Prostaglandin production
Cytokine activity
Nitric oxide production
Matrix metalloproteinases
Aggrecan-degrading enzymes
These actions may help explain why clinical trials have found improvements in pain, stiffness, function, and swelling rather than only structural outcomes.
5. They Work Slowly
Glucosamine and chondroitin are generally categorized as slow-acting agents. They do not work like aspirin, ibuprofen, or an anesthetic. Their effects tend to develop gradually as joint metabolism, inflammatory signaling, and tissue turnover change. Most meaningful clinical trials have lasted from 3 months and as long as several years.
What the Human Research Shows for Glucosamine Sulfate
After three years, the placebo group had lost an average of 0.31 millimeters of joint-space width, while the glucosamine-sulfate group had no statistically significant mean joint-space loss, with a change of 0.06 millimeters. Symptoms measured by the WOMAC osteoarthritis index also worsened slightly in the placebo group while improving in the glucosamine group. This trial is especially important because it evaluated more than short-term pain. It examined symptoms and radiographic joint structure over three years.
The six-month GUIDE trial evaluated1,500 mg of prescription glucosamine sulfate once daily in adults with knee osteoarthritis. Glucosamine sulfate produced a significantly greater improvement in pain, function, and disability.
Aside from the above research, many other studies have shown positive pain benefits for patients taking 1500 mg of glucosamine daily.
What the Human Research Shows for Chondroitin Sulfate
A Cochrane review evaluated randomized trials of chondroitin used alone or with glucosamine. Compared with placebo, chondroitin produced improvements in pain and functionality.
Another study called The CONCEPT trial, was a six-month, randomized, double-blind study involving 604 adults with symptomatic knee osteoarthritis. The study compared chondroitin to the prescription pain drug, Celecoxib, and a placebo. Chondroitin sulfate was superior to placebo for reducing pain and improving physical function. Its effects were comparable to celecoxib.
A one-year, randomized, double-blind pilot study included 42 adults with symptomatic knee osteoarthritis. 800 mg of chondroitin significantly reduced joint pain and improved mobility. The study also showed that chondroitin preserved the joint space of the knee.
A multicenter, randomized, double-blind, placebo-controlled study evaluated intermittent chondroitin-sulfate treatment for one year in people with knee osteoarthritis. The trial reported symptomatic benefits and supported the use of chondroitin as a slow-acting osteoarthritis intervention.
This was the dose used in major long-term knee-osteoarthritis trials and across most studies included in the glucosamine-sulfate umbrella review.
Chondroitin Sulfate
Positive studies commonly used:
800 to 1,200 mg daily
How Long Does It Take to Work?
Glucosamine and chondroitin should be evaluated as slow-acting joint-support compounds.
Positive studies reported benefits over:
Four months
Six months
One year
Three years
The MOVES trial demonstrated that the combination gradually reached outcomes comparable to celecoxib by six months. The long-term glucosamine-sulfate trial evaluated joint-space width and symptoms over three years.
A practical trial should generally last at least three to six months, provided the product, dose, and formulation resemble those used in positive research.
Stopping after one or two weeks does not meaningfully test a slow-acting cartilage-support strategy.
Who May Benefit Most?
Glucosamine and chondroitin may be especially useful for people who:
Have mild-to-moderate knee osteoarthritis
Experience chronic pain and stiffness rather than an acute injury
Want support for cartilage metabolism in addition to pain relief
Prefer a slow-acting nutritional strategy
Are willing to use a studied dose consistently
Are early enough in the disease process to retain meaningful cartilage
Want to combine structural support with exercise and an anti-inflammatory diet
Have hand osteoarthritis, particularly when considering chondroitin sulfate
The strongest direct research concerns knee osteoarthritis, with additional positive evidence for chondroitin in hand osteoarthritis.
When Glucosamine and Chondroitin Make the Most Sense
These supplements make the most biological sense when they are used as part of a strategy that reduces ongoing joint damage.
That includes:
Improving muscle strength around the joint
Correcting movement mechanics
Reducing excess body weight when appropriate
Stabilizing blood sugar
Removing inflammatory foods
Eating adequate protein
Correcting vitamin C and other nutrient insufficiencies
Avoiding repetitive mechanical overload
Maintaining regular low-impact movement
Supplying cartilage-related nutrients while continuing to expose the joint to poor mechanics, sugar overload, inactivity, and chronic inflammation limits what any supplement can accomplish.
Glucosamine and Chondroitin Research Summary
Evidence category
What positive human research supports
Knee pain
Improved in multiple trials and evidence reviews
Stiffness
Improved in glucosamine-chondroitin combination trials
Physical function
Improved with glucosamine sulfate, chondroitin sulfate, and selected combinations
Comparison with celecoxib
Combination and pharmaceutical-grade chondroitin produced comparable outcomes in major trials
Hand osteoarthritis
Chondroitin improved pain, function, grip strength, and morning stiffness
Joint swelling
Improved in the MOVES combination trial
Joint-space narrowing
Slower loss reported in selected long-term glucosamine- and chondroitin-sulfate trials
Cartilage regeneration
Not established
Most studied glucosamine form
Crystalline glucosamine sulfate
Common glucosamine dose
1,500 mg daily
Common chondroitin dose
800–1,200 mg daily
Expected timeline
Usually several months
Product-quality importance
High
Key Takeaways
Glucosamine and chondroitin are different compounds that support overlapping aspects of joint biology.
Glucosamine is involved in pathways used to produce glycosaminoglycans and proteoglycans. Chondroitin sulfate is a structural component of cartilage that helps the tissue attract water and resist compression.
Positive human trials support benefits for:
Pain
Stiffness
Mobility
Physical function
Joint swelling
Hand function
Long-term joint-space preservation in selected studies
The strongest glucosamine evidence centers on 1,500 mg of crystalline glucosamine sulfate daily. The strongest chondroitin studies commonly used 800 to 1,200 mg of standardized pharmaceutical-grade chondroitin sulfate.
These nutrients are not fast painkillers. They are slow-acting compounds that should be used consistently and evaluated over three to six months or longer. Product quality determines whether the bottle in someone’s hand resembles the formulation used in research. The name “glucosamine and chondroitin” on the front label is not enough. The form, dose, purity, standardization, and manufacturing quality all influence whether the supplement has a realistic chance of reproducing clinical results.
In my clinical practice, I commonly recommend a combination formula that contains glucosamine, chondroitin, and MSM. This combination of ingredients very commonly reduces the pain and stiffness for many of my patients.
Supplement #4: Boswellia
A Fast-Acting Botanical for Osteoarthritis Pain, Stiffness, and Function
Boswellia serrata, commonly known as Indian frankincense, has been used traditionally for inflammatory conditions for centuries. Modern research has focused on concentrated extracts from the plant’s gum resin, particularly standardized preparations rich in boswellic acids.
For osteoarthritis, the human evidence is surprisingly strong.
Randomized controlled trials have reported improvements in:
Knee pain
Joint stiffness
Walking ability
Physical function
WOMAC scores
Lequesne Functional Index scores
Joint swelling in some studies
Several trials have also reported improvements within the first week of supplementation, making Boswellia one of the faster-acting supplements discussed in this article.
A 2020 systematic review and meta-analysis of seven randomized controlled trials involving 545 people with osteoarthritis found that Boswellia significantly improved pain, stiffness, and physical function.
What Is Boswellia?
Boswellia serrata is a tree native to India, North Africa, and parts of the Middle East. Its resin contains a group of pentacyclic triterpenes collectively known as boswellic acids.
The compounds that receive the most research attention include:
Boswellia extracts differ substantially in their composition and concentration of boswellic acids. Many of the positive clinical trials have evaluated standardized formulations rather than generic Boswellia powders. Some of the best-studied preparations include:
Boswellia is often described as a “natural 5-LOX inhibitor.” There is some truth to that, but the biology is more complicated than the marketing slogan. The enzyme 5-lipoxygenase, or 5-LOX, participates in the conversion of arachidonic acid into leukotrienes, inflammatory lipid mediators involved in immune signaling.
AKBA has demonstrated direct interactions with 5-LOX in laboratory studies. Early research showed that AKBA could influence 5-LOX activity through an allosteric mechanism rather than by competing directly with arachidonic acid at the enzyme’s active site. (Review the mechanistic research)
More recent structural research has confirmed that AKBA binds to an allosteric region of 5-LOX and can alter the enzyme’s activity and the pattern of lipid products it generates. (Review the structural research)
However, pharmacokinetic research has raised an important point: circulating concentrations of AKBA after ordinary oral Boswellia supplementation may be much lower than the concentrations required to reproduce some laboratory effects. Other boswellic acids, including β-boswellic acid, reach higher circulating concentrations and may influence additional inflammatory enzymes. (Read the pharmacology review)
Bottom line: Boswellia contains multiple boswellic acids that influence several inflammatory pathways, including 5-LOX-related signaling, prostaglandin pathways, proteolytic enzymes, and inflammatory cellular responses.
2. Boswellia May Reduce Cartilage-Degrading Enzymes
Osteoarthritis involves increased activity of enzymes capable of degrading the cartilage matrix. One of these is matrix metalloproteinase-3, or MMP-3. MMP-3 can participate in breakdown of:
Proteoglycans
Fibronectin
Other extracellular-matrix proteins
A 90-day randomized trial evaluating 5-Loxin measured MMP-3 directly in the synovial fluid of people with knee osteoarthritis. The higher-dose Boswellia group showed a significant reduction in synovial-fluid MMP-3, providing human evidence that this extract may influence a biological pathway associated with cartilage degradation.
3. Boswellia May Reduce Systemic Inflammatory Markers
A more recent randomized, double-blind, placebo-controlled trial evaluated an enhanced-bioavailability Boswellia extract called Aflapin in people with knee osteoarthritis. After 30 days, the Boswellia group showed reductions in several circulating markers associated with inflammation and cartilage turnover, including:
TNF-α
High-sensitivity CRP
MMP-3
C2C, a marker of type II collagen breakdown
At the same time, participants experienced significant improvements in pain, stiffness, and function.
4. Boswellia Can Improve Pain Without Acting Like a Conventional NSAID
NSAIDs primarily work by interfering with cyclooxygenase enzymes and prostaglandin production. Boswellia interacts with a broader and somewhat different network of inflammatory pathways. This makes Boswellia particularly interesting as part of a multi-target strategy. Turmeric, omega-3 fats, Boswellia, glucosamine, chondroitin, and vitamin C do not simply duplicate one another.
Boswellia appears especially useful for targeting:
Inflammatory lipid signaling
Joint pain
Stiffness
MMP activity
Physical function
Synovial inflammatory activity
What the Human Research Shows
A 2020 systematic review and meta-analysis evaluated seven randomized controlled trials involving 545 osteoarthritis patients. Compared with placebo or conventional treatment, Boswellia significantly improved pain, stiffness, and joint function. The authors concluded that Boswellia extracts may be effective and safe for osteoarthritis and found that improvements generally became apparent after at least four weeks of treatment.
One of the earliest controlled human trials evaluated Boswellia serrata extract in 30 people with knee osteoarthritis using a randomized, double-blind, placebo-controlled crossover design. Participants received Boswellia extract or placebo for eight weeks before crossing over to the alternate treatment. During Boswellia treatment, participants experienced reduced knee pain, increased range of motion, improved walking distance, and reduced knee swelling.
A 2008 randomized, double-blind, placebo-controlled trial evaluated 75 adults with knee osteoarthritis. The patients reported improvements in both pain and physical function. Patients receiving 250 mg doses experienced relief is as little as seven days. Boswellia also led to reduced inflammation markers in the synovial fluid of patients taking it.
A 2023 randomized, double-blind, placebo-controlled trial involving 70 adults with knee osteoarthritis who were given 100 mg of boswellia extract (aflapin) daily for 30 days. The outcomes were impressive. Patients reported less pain, stuffness, improved joint function, and follow up labs showed reductions in inflammatory markers.
Taken together, the available human data support a consistent pattern. Boswellia extracts can reduce osteoarthritis pain, improve stiffness, and improve physical function.
How Much Boswellia Was Used in Positive Human Studies?
Human trial doses varied between 100 mg/day and 250 mg/day.
How Fast Can Boswellia Work?
Research studies show pain relief in less than a week of use. In my experience, relief can happen much more quickly for some. Especially at higher doses and when mixed with white willow. Many patients report pain relief within hours of use.
Key Takeaways
Boswellia has some of the most compelling human evidence among botanical supplements for osteoarthritis. It is one of the fastest working natural compounds when it comes to pain relief.
Supplement #5: Vitamin C
An Essential Nutrient for Collagen Production, Cartilage Integrity, and Antioxidant Defense
Vitamin C is rarely marketed as an arthritis supplement, but from a biological standpoint, it is one of the most important nutrients for connective tissue. Your body cannot make collagen properly without it. Important because collagen is one of the primary structural proteins in cartilage, tendons, ligaments, bone, and other tissues that stabilize and protect joints. Vitamin C is also a major antioxidant that helps protect cartilage cells from oxidative stress.
For osteoarthritis, the human evidence is not as extensive as the evidence for curcumin or Boswellia. There are fewer randomized controlled trials specifically testing vitamin C as a treatment for OA pain. But the available human data are positive and biologically compelling.
Human studies have reported:
Reduced osteoarthritis pain with calcium ascorbate
Better functional scores
Lower risk of cartilage loss with higher vitamin C intake
Lower risk of knee OA progression in a major longitudinal cohort
Associations between higher vitamin C intake and healthier cartilage MRI characteristics
Vitamin C also plays a direct, non-negotiable role in the chemistry of collagen formation.
Why Vitamin C Is So Important for Your Joints
Cartilage is made largely from:
Water
Type II collagen
Proteoglycans
Glycosaminoglycans
Specialized cartilage cells called chondrocytes
The collagen framework gives cartilage tensile strength and structural organization. Proteoglycans trap water inside that framework, allowing cartilage to absorb compression. If collagen production is impaired, the tissue itself becomes structurally weaker. Vitamin C participates directly in that process.
These enzymes modify the amino acids proline and lysine during collagen synthesis. That hydroxylation process allows newly produced collagen chains to form the stable triple-helix structure characteristic of mature collagen. Without adequate vitamin C, collagen cannot be assembled and stabilized normally. This biology is not theoretical. Severe vitamin C deficiency causes scurvy, a disease characterized by defective collagen production resulting in bleeding gums, fragile blood vessels, poor wound healing, musculoskeletal pain, and connective-tissue failure.
2. Vitamin C Supports Cartilage Matrix Production
Collagen is only part of cartilage.
Healthy cartilage also contains large proteoglycan molecules that help retain water and absorb pressure. Vitamin C is essential not only in collagen formation but also in glycosaminoglycan and proteoglycan metabolism, both central components of the cartilage extracellular matrix.
This means vitamin C potentially supports both major sides of cartilage structure:
Mechanical stress, inflammation, mitochondrial dysfunction, and inflammatory cytokines can increase production of reactive oxygen species.
These molecules can damage:
Chondrocytes
Collagen
Proteoglycans
Cell membranes
Mitochondria
DNA
Vitamin C is a water-soluble antioxidant capable of donating electrons to reactive molecules and helping neutralize oxidative stress. It also interacts with other antioxidant systems in the body. This is especially relevant because oxidative stress and inflammation can reinforce one another. Free radicals can amplify inflammatory signaling, while inflammation creates more reactive oxygen species. Vitamin C therefore plays two complementary roles:
Structural
Supporting collagen formation.
Protective
Helping defend connective tissue against oxidative damage.
What the Human Research Shows
One of the few direct randomized human trials of vitamin C for osteoarthritis was conducted in 133 people with radiographically confirmed symptomatic osteoarthritis of the hip and/or knee. The vitamin C treatment also produced a statistically significant improvement in the Lequesne Functional Index, a measure of pain, walking ability, and daily function. Patients also experienced modest pain relief.
Some of the most interesting vitamin C findings come from the Framingham cohort. Researchers evaluated 640 people and compared dietary antioxidant intake with the development and progression of knee osteoarthritis. Higher vitamin C intake was strongly associated with a lower risk of osteoarthritis progression. Participants with higher vitamin C intake also had a significantly lower risk of developing knee pain. The authors concluded that higher antioxidant intake, particularly vitamin C, may reduce cartilage loss and osteoarthritis progression.
An analysis from the Osteoarthritis Initiative studied 1,785 people with knee osteoarthritis. Researchers evaluated vitamin C intake along with MRI measurements. Higher vitamin C intake was associated with healthier cartilage.
Why Vitamin C May Be Especially Important When Taking Collagen
Later in this article, collagen appears as an honorable mention supplement. There is an important biological connection between collagen supplementation and vitamin C. Collagen supplements provide amino acids and peptides that the body can use in connective-tissue metabolism. But supplying collagen peptides does not eliminate the need for the cofactors required to process and stabilize newly synthesized collagen. Vitamin C remains necessary.
Vitamin C and Chondrocytes
Chondrocytes are the cells responsible for maintaining cartilage.
They produce:
Type II collagen
Aggrecan
Proteoglycans
Other components of the extracellular matrix
These cells must maintain a constant balance between tissue breakdown and tissue rebuilding. Vitamin C supports several aspects of this process because it participates in collagen synthesis and protects cells against oxidative stress. This creates an important nutritional principle: Cartilage cannot maintain itself efficiently without the nutrients required for cartilage production.
Pain relief is important, but joint nutrition should also address what cartilage actually needs to function.
Vitamin C From Food
Unlike most animals, humans cannot manufacture vitamin C internally.
We must obtain it through food or supplementation.
Good food sources include:
Bell peppers
Broccoli
Brussels sprouts
Strawberries
Kiwi
Citrus fruit
Cabbage
Cauliflower
Leafy greens
Acerola cherry
Camu camu
Vitamin C is sensitive to heat, storage, oxygen, and food processing. Long cooking times can substantially reduce the vitamin C content of vegetables. For this reason, consuming a combination of raw and lightly cooked vitamin C-rich foods can help preserve intake.
How Much Vitamin C Should You Take? Who May Benefit the Most?
Unlike curcumin, Boswellia, glucosamine, or chondroitin, the osteoarthritis literature does not establish a universally validated therapeutic vitamin C dose. That being said, vitamin C need doses can range dramatically from one person to the next. In my clinical practice, I use doses ranging from 1-20 grams daily depending on patient needs and responses. I often pair higher doses of vitamin C with the bioflavonoid, quercetin (3-4 grams daily). As a general rule, I find that the dietary and social history of a person provides relevance for establishing an initial dose recommendation.
The following are factors I use to help determine dose:
Vitamin C requirements are typically much higher when the above conditions are present.
Vitamin C Research Summary
Evidence Category
What Verified Human Research Supports
Osteoarthritis pain
Improved modestly in one randomized crossover trial
Physical function
Lequesne score improved in the randomized trial
Cartilage loss
Higher intake associated with lower risk in Framingham data
OA progression
Higher intake associated with substantially lower progression risk in Framingham
Knee pain development
Lower risk associated with higher vitamin C intake
Incident knee OA
Supplement users had lower risk in a longitudinal study
Cartilage MRI characteristics
Higher intake associated with more favorable measures
Collagen synthesis
Vitamin C is an essential biochemical cofactor
Antioxidant activity
Well established
Proven cartilage regeneration
Not established
Universal OA treatment dose
Not established
Strength of OA intervention evidence
Limited but positive
Key Takeaways
Vitamin C is one of the most overlooked nutrients in osteoarthritis. It is required for the enzymes that stabilize collagen, participates in cartilage-matrix biology, and provides antioxidant protection against oxidative stress. You cannot build normal collagen without vitamin C.
Honorable Mentions
Four Additional Supplements Worth Considering
The five supplements covered in this article have the strongest combination of biological plausibility and positive human clinical evidence for osteoarthritis. They consistently rank among the most studied nutritional interventions for reducing pain, improving physical function, and supporting healthier joint biology.
That does not mean they are the only supplements that may be helpful.
Several additional nutrients and botanical compounds have shown encouraging results in human studies. They simply do not yet have the same depth, consistency, or quantity of evidence as the top five.
For some people, these supplements may work particularly well when combined with the foundational strategies discussed throughout this article.
Collagen Peptides
Supplying the Building Blocks for Cartilage
Collagen is the most abundant protein in the human body and one of the primary structural components of cartilage, tendons, ligaments, bone, skin, and connective tissue. Articular cartilage consists primarily of type II collagen, organized into a strong network that provides tensile strength while supporting the water-rich proteoglycan matrix that absorbs compression. Unlike glucosamine and chondroitin, which support cartilage matrix chemistry, collagen supplements provide peptides and amino acids that may stimulate cartilage-producing cells and support connective-tissue metabolism.
What the Human Research Shows
A 2018 systematic review evaluating collagen supplementation for osteoarthritis concluded that collagen hydrolysates and undenatured type II collagen improved joint pain and physical function in several randomized controlled trials.
More recently, a 2023 systematic review and meta-analysis reported that collagen supplementation significantly improved WOMAC pain, stiffness, physical function, and overall WOMAC scores in people with knee osteoarthritis. The analysis also found improvements in visual analog pain scores compared with placebo.
Dr. Osborne’s Experience
My Clinical experience using collagen has been overall good. It is easy to take and well tolerated by the vast majority of patients, and outcomes are typically very positive.
B-Vitamins
Supporting Joint Metabolism and Pain Pathways
B vitamins are rarely promoted as osteoarthritis supplements, yet they participate in hundreds of metabolic reactions that influence connective tissue, nerve function, energy production, methylation, and inflammation. Vitamin B6 is involved in amino acid metabolism needed for collagen production. Vitamin B12 and folate help regulate homocysteine, an amino acid associated with connective-tissue damage and impaired collagen cross-linking when chronically elevated. Deficiencies in B vitamins can also contribute to peripheral nerve dysfunction, potentially amplifying pain perception independent of structural joint damage.
What the Human Research Shows
Dr. Osborne’s Experience
B-vitamins are essential in helping the body produce the energy needed to maintain and repair the joints and surrounding tissues. They represent one of the most common deficiencies I see in patients, and correcting deficits contributes to improved health all around. I have seen a number of cases where B-vitamin deficits were directly responsible for a patients pain.
Quercetin
A Powerful Plant Flavonoid With Emerging Human Evidence
Quercetin is a naturally occurring flavonoid found in onions, apples, capers, berries, kale, and many other plant foods. It has attracted growing scientific interest because of its antioxidant and anti-inflammatory properties. Laboratory research suggests quercetin influences NF-κB signaling, inflammatory cytokines, oxidative stress, and cartilage-degrading enzymes.
What the Human Research Shows
A randomized, double-blind, placebo-controlled trial found that quercetin supplementation significantly improved WOMAC pain, stiffness, physical function, and total WOMAC scores in women with knee osteoarthritis after eight weeks. Participants also demonstrated reductions in inflammatory biomarkers compared with placebo.
Dr. Osborne’s Experience
Quercetin has been an important part of my nutritional arsenal for patients struggling with chronic pain. I have been using it for several decades to help people find improved pain relief. It works best when combined with higher doses of vitamin C (as discussed above).
White Willow Bark
Nature’s Original Salicin Source
Long before aspirin was developed, extracts from willow bark were used to relieve pain and fever. White willow bark naturally contains salicin, a compound that is converted in the body into salicylic acid derivatives. Unlike aspirin, however, willow bark contains numerous additional polyphenols and plant compounds that may contribute to its overall activity.
What the Human Research Shows
Dr. Osborne’s Experience
I have seen many patients respond very well to white willow extracts without experiencing the traditional GI side effects from NSAIDS. It works better when combined with boswellia extract, and I keep it in my arsenal of supplements to use to support patients who struggle with chronic osteoarthritis pain.
The Bottom Line
No single supplement is likely to eliminate osteoarthritis pain by itself. The strongest strategy combines nutrients that address different aspects of joint biology. For many people, that means building a foundation with omega-3 fatty acids, curcumin, glucosamine, chondroitin sulfate, Boswellia, and vitamin C while selectively adding collagen, quercetin, B vitamins, or white willow bark when appropriate.
The greatest improvements usually occur when targeted supplementation is paired with an anti-inflammatory diet, progressive strength training, healthy body composition, adequate sleep, and correction of nutrient deficiencies. Supplements work best when they support an environment that allows joints to recover rather than continually breaking them down.
The Missing Piece: Why Your Diet Determines Whether Supplements Succeed
Supplements work best when they are used within a dietary environment that supports tissue repair rather than continually promoting inflammation and metabolic stress.
One of the central messages in my internationally best selling book, No Grain No Pain, is that chronic pain is rarely the result of a single deficiency or one damaged joint. It develops within an inflammatory environment created by years of poor dietary habits, excess sugar, nutrient deficiencies, sedentary living, excess body fat, repetitive joint stress, and in some individuals, adverse immune reactions to foods such as gluten. If you continue feeding inflammation every day, even the best supplements will have limited success.
Osteoarthritis Is More Than “Wear and Tear”
As discussed earlier, osteoarthritis is not simply a mechanical “wear and tear” condition. Inflammation, oxidative stress, metabolic dysfunction, and abnormal joint remodeling all contribute to disease progression. That matters nutritionally because diet can influence several of those same biological processes.
Sugar Doesn’t Just Affect Blood Sugar, It Changes Your Cartilage
Most people understand that excessive sugar increases the risk of diabetes. Far fewer realize that high blood sugar also changes the physical properties of cartilage. Glucose readily attaches to proteins through a process called glycation. Over time these reactions produce compounds known as advanced glycation end products, or AGEs. Think of AGEs as microscopic chemical cross-links that slowly stiffen collagen.
Cartilage is designed to be flexible. Every step, squat, and jump compresses cartilage and then allows it to rebound. When AGEs accumulate within the collagen framework, cartilage becomes less resilient, less elastic, and more vulnerable to mechanical damage. AGEs also influence chondrocytes, the cells responsible for maintaining cartilage, promoting inflammatory signaling and reducing normal tissue maintenance. This combination of increased stiffness and altered cell function is believed to contribute to osteoarthritis progression.
The practical message is simple:
A diet that continually spikes blood sugar doesn’t just affect your waistline. It changes the chemistry of your joints.
Processed Grains Feed More Than Blood Sugar
Refined grains deserve special attention because they are one of the largest sources of rapidly absorbed carbohydrate in the modern diet.
White bread.
Breakfast cereal.
Crackers.
Pretzels.
Cookies.
Pastries.
Many gluten-free processed foods.
These foods digest quickly, producing repeated elevations in blood glucose and insulin while contributing relatively few of the vitamins, minerals, antioxidants, and amino acids needed to maintain healthy connective tissue. Replacing refined grains with nutrient-dense whole foods increases protein, vitamins, minerals, phytonutrients, and healthy fats while reducing the glycemic burden placed on the body.
Protein Is the Raw Material for Joint Repair
Cartilage cannot repair itself without amino acids. Neither can tendons. Neither can ligaments. Every structural protein in your joints must be synthesized from dietary amino acids. This is one reason many highly processed grain-based diets perform poorly from a musculoskeletal standpoint. They often provide abundant calories but relatively little high-quality protein.
Supplements such as glucosamine, chondroitin, collagen peptides, vitamin C, and Boswellia work best when the body has the raw materials required to rebuild connective tissue. Without adequate protein, even the best supplement protocol becomes less effective.
The Gluten Connection
For most people with osteoarthritis, gluten is probably not the primary cause of cartilage degeneration. However, there is an important exception. People with celiac disease and some individuals with non-celiac gluten sensitivity can develop musculoskeletal problems that either mimic osteoarthritis or worsen existing joint disease. This distinction is important. If someone has untreated celiac disease, removing gluten does much more than improve digestion. It can reduce chronic immune activation, improve nutrient absorption, support bone health, and improve musculoskeletal symptoms.
Celiac Disease Is a Systemic Disease, Not Just a Digestive Disorder
For years, celiac disease was viewed primarily as an intestinal disorder. That view has changed dramatically. Modern research recognizes celiac disease as a systemic immune-mediated disease capable of affecting nearly every organ system.
A recent comprehensive review concluded that celiac disease has profound effects on bone, muscle, and joint health through chronic inflammation, immune dysregulation, intestinal injury, alterations in the gut microbiome, and nutritional deficiencies. The review describes increased risks of osteoporosis, fractures, sarcopenia, muscle weakness, functional decline, and joint disorders while emphasizing that treatment should include a strict gluten-free diet together with nutritional rehabilitation and physical restoration. In other words, the small intestine may be where celiac disease begins. It is not where it ends.
Joint Pain May Be the First Symptom
Many people assume celiac disease always causes diarrhea and weight loss. It often does not. Musculoskeletal symptoms can appear before significant digestive complaints.
A 2025 systematic review and meta-analysis reported that approximately 10.7% of individuals with celiac disease experienced joint manifestations even without another diagnosed rheumatic disease. The authors concluded that joint symptoms are a common extra-intestinal manifestation of celiac disease and deserve greater clinical recognition. Other reviews describe arthralgia, inflammatory arthritis, osteoporosis, osteomalacia, muscle weakness, and chronic musculoskeletal pain as well-recognized manifestations of celiac disease and, in some cases, non-celiac gluten sensitivity.
Why Nutrient Deficiencies Matter
Healthy cartilage requires nutrients.
Healthy bone requires nutrients.
Healthy muscle requires nutrients.
Untreated celiac disease damages the lining of the small intestine, the very tissue responsible for absorbing those nutrients. As a result, deficiencies of vitamin D, calcium, magnesium, iron, zinc, vitamin B12, folate, and other essential nutrients are common. These deficiencies affect much more than laboratory values. They influence muscle strength, Bone density, Collagen production, Energy metabolism, Recovery, Balance, and ultimately the body’s ability to maintain healthy joints.
Why the No Grain No Pain Approach Makes Sense
The goal of No Grain No Pain is not simply to eliminate one ingredient. The goal is to remove foods that commonly contribute to inflammation while replacing them with foods that provide the nutrients required for healing.
That means emphasizing:
High-quality protein
Organic vegetables
Healthy fats
Omega-3-rich seafood
Nuts and seeds (when tolerated)
Herbs and spices
Whole foods
while eliminating:
Refined grains
Ultra-processed foods
Sugar-sweetened beverages
Excess added sugar
Industrial seed oils used in heavily processed foods
Foods that trigger immune reactions in susceptible individuals
This approach naturally complements the supplements discussed throughout this article. Omega-3 fats become part of a healthier dietary fat pattern. Vitamin C is obtained from vegetables as well as supplements. Curcumin becomes one component of an anti-inflammatory dietary strategy rather than a substitute for one. Glucosamine and chondroitin support cartilage that is no longer being exposed to the same degree of metabolic stress. Boswellia helps calm inflammatory pathways while diet works to reduce the ongoing signals driving them. The result is synergy. Instead of asking one supplement to overcome years of dietary injury, you create an environment where every intervention has a greater opportunity to work.
Practical No Grain No Pain Guidelines for Osteoarthritis
If your goal is to reduce osteoarthritis pain naturally, begin with the foundation.
Remove grains and ultra-processed grain products.
Eliminate gluten completely if you have celiac disease or confirmed gluten sensitivity.
Base meals around high-quality protein and non-starchy vegetables.
Eat fatty fish regularly or use a clinically studied omega-3 supplement.
Replace sugary snacks with whole-food sources of healthy fats and protein.
Increase intake of vitamin C-rich vegetables to support collagen production.
Use herbs and spices such as turmeric as part of your daily cooking.
Maintain a healthy body weight to reduce both inflammatory burden and mechanical stress on weight-bearing joints.
The Bottom Line
Supplements can reduce pain. They can improve function. They can support cartilage metabolism. But they cannot overcome a diet that continually fuels inflammation and deprives joints of the nutrients they need to maintain themselves. The most successful long-term strategy is not choosing between nutrition and supplementation. It is combining both. When you remove dietary factors that promote inflammation and replace them with nutrient-dense whole foods, you create the biological environment that allows supplements and your own natural repair mechanisms to perform at their best.