


There is a particular kind of dread that arrives with overhead lighting. You catch yourself in a lift mirror, or in the front-facing camera you didn’t mean to open, and the crown is doing something it wasn’t doing two years ago. The options at that point feel binary and both feel bad: do nothing, or consider a hair transplant.
The category between those two poles has quietly become the most interesting part of men’s grooming. The treatment I had in April sits in the middle of it: Autologous Micrografting Technology – AMT – the thing behind the “stem cell and exosome” language. I had it at Ouronyx on St James’s Street on 09/04/26. Here’s what it is, what happened, and what I can and can’t honestly claim about the results.
What a stem cell and exosome hair treatment actually is
Strip the marketing away and AMT is a tissue transfer, not a drug and not a transplant.
A doctor takes two or three tiny punches of skin – around 2.5mm, from the mastoid area behind the ear or the nape, chosen because that hair is genetically resistant to the hormone that causes male pattern baldness. That tissue goes into a device that mechanically breaks it down and filters it into a liquid suspension: progenitor cells, growth factors and the signalling vesicles known as exosomes, all of them yours.
That suspension is then injected across the thinning areas in a grid of small mesotherapy-style points. Start to finish it’s a single appointment. Nothing is cultured, nothing is frozen, nothing arrives in a vial from elsewhere.
The mechanism, as far as the literature understands it, isn’t that new hair is created. It’s signalling. The suspension delivers cytokines and growth factors that suppress follicle cell death, dampen inflammation and encourage new blood supply, while the exosomes appear to carry messages between hair follicle stem cells and the dermal papilla cells that govern the growth cycle. In plain terms: you are not adding hair, you are talking struggling follicles out of retiring.
The clinic’s own framing goes a step further than that.
“Micrografting Technology is the ability of micrografts to stimulate the dormant hair follicular units, reverting the shrinking process typical in Androgenetic Alopecia and thereby inducing the development of new hair follicles,” says Dr. Marco Nicoloso, Medical Director at Ouronyx in London. “It uses tiny samples of the patient’s own skin tissue, left completely unaltered, containing the same natural components already present in the body – allowing them to be easily recognised and accepted when reintroduced into the scalp.”
“The foundation of this treatment is the transplantation of mature multipotent stem cells in the balding areas, reinstating the hair growth signalling via the injection of stem cells and growth factors, thereby enabling hair follicle regeneration.”
The “left completely unaltered” part is the bit worth underlining, and I’ll come back to it, because it’s the whole regulatory story.
On the development of new follicles, though, I’d add a note – and Ouronyx’s own press material adds it for me. Their launch release for the treatment states plainly: “It is important to understand that Micrografting won’t create new hair on your scalp. But it will encourage existing follicles to grow, so sparse areas on the scalp will become thicker and fuller.” That is the more conservative claim, it is the one the published evidence supports, and it is the one I’d go in expecting. Reversing miniaturisation is well established as a mechanism. Generating genuinely new follicles is a bigger claim than the trial data currently carries.
Either way, the distinction that matters most before you spend any money is this. A transplant moves hair. AMT tries to save the hair you still have. If you are already bald on top, this is not your treatment.
What the appointment was actually like
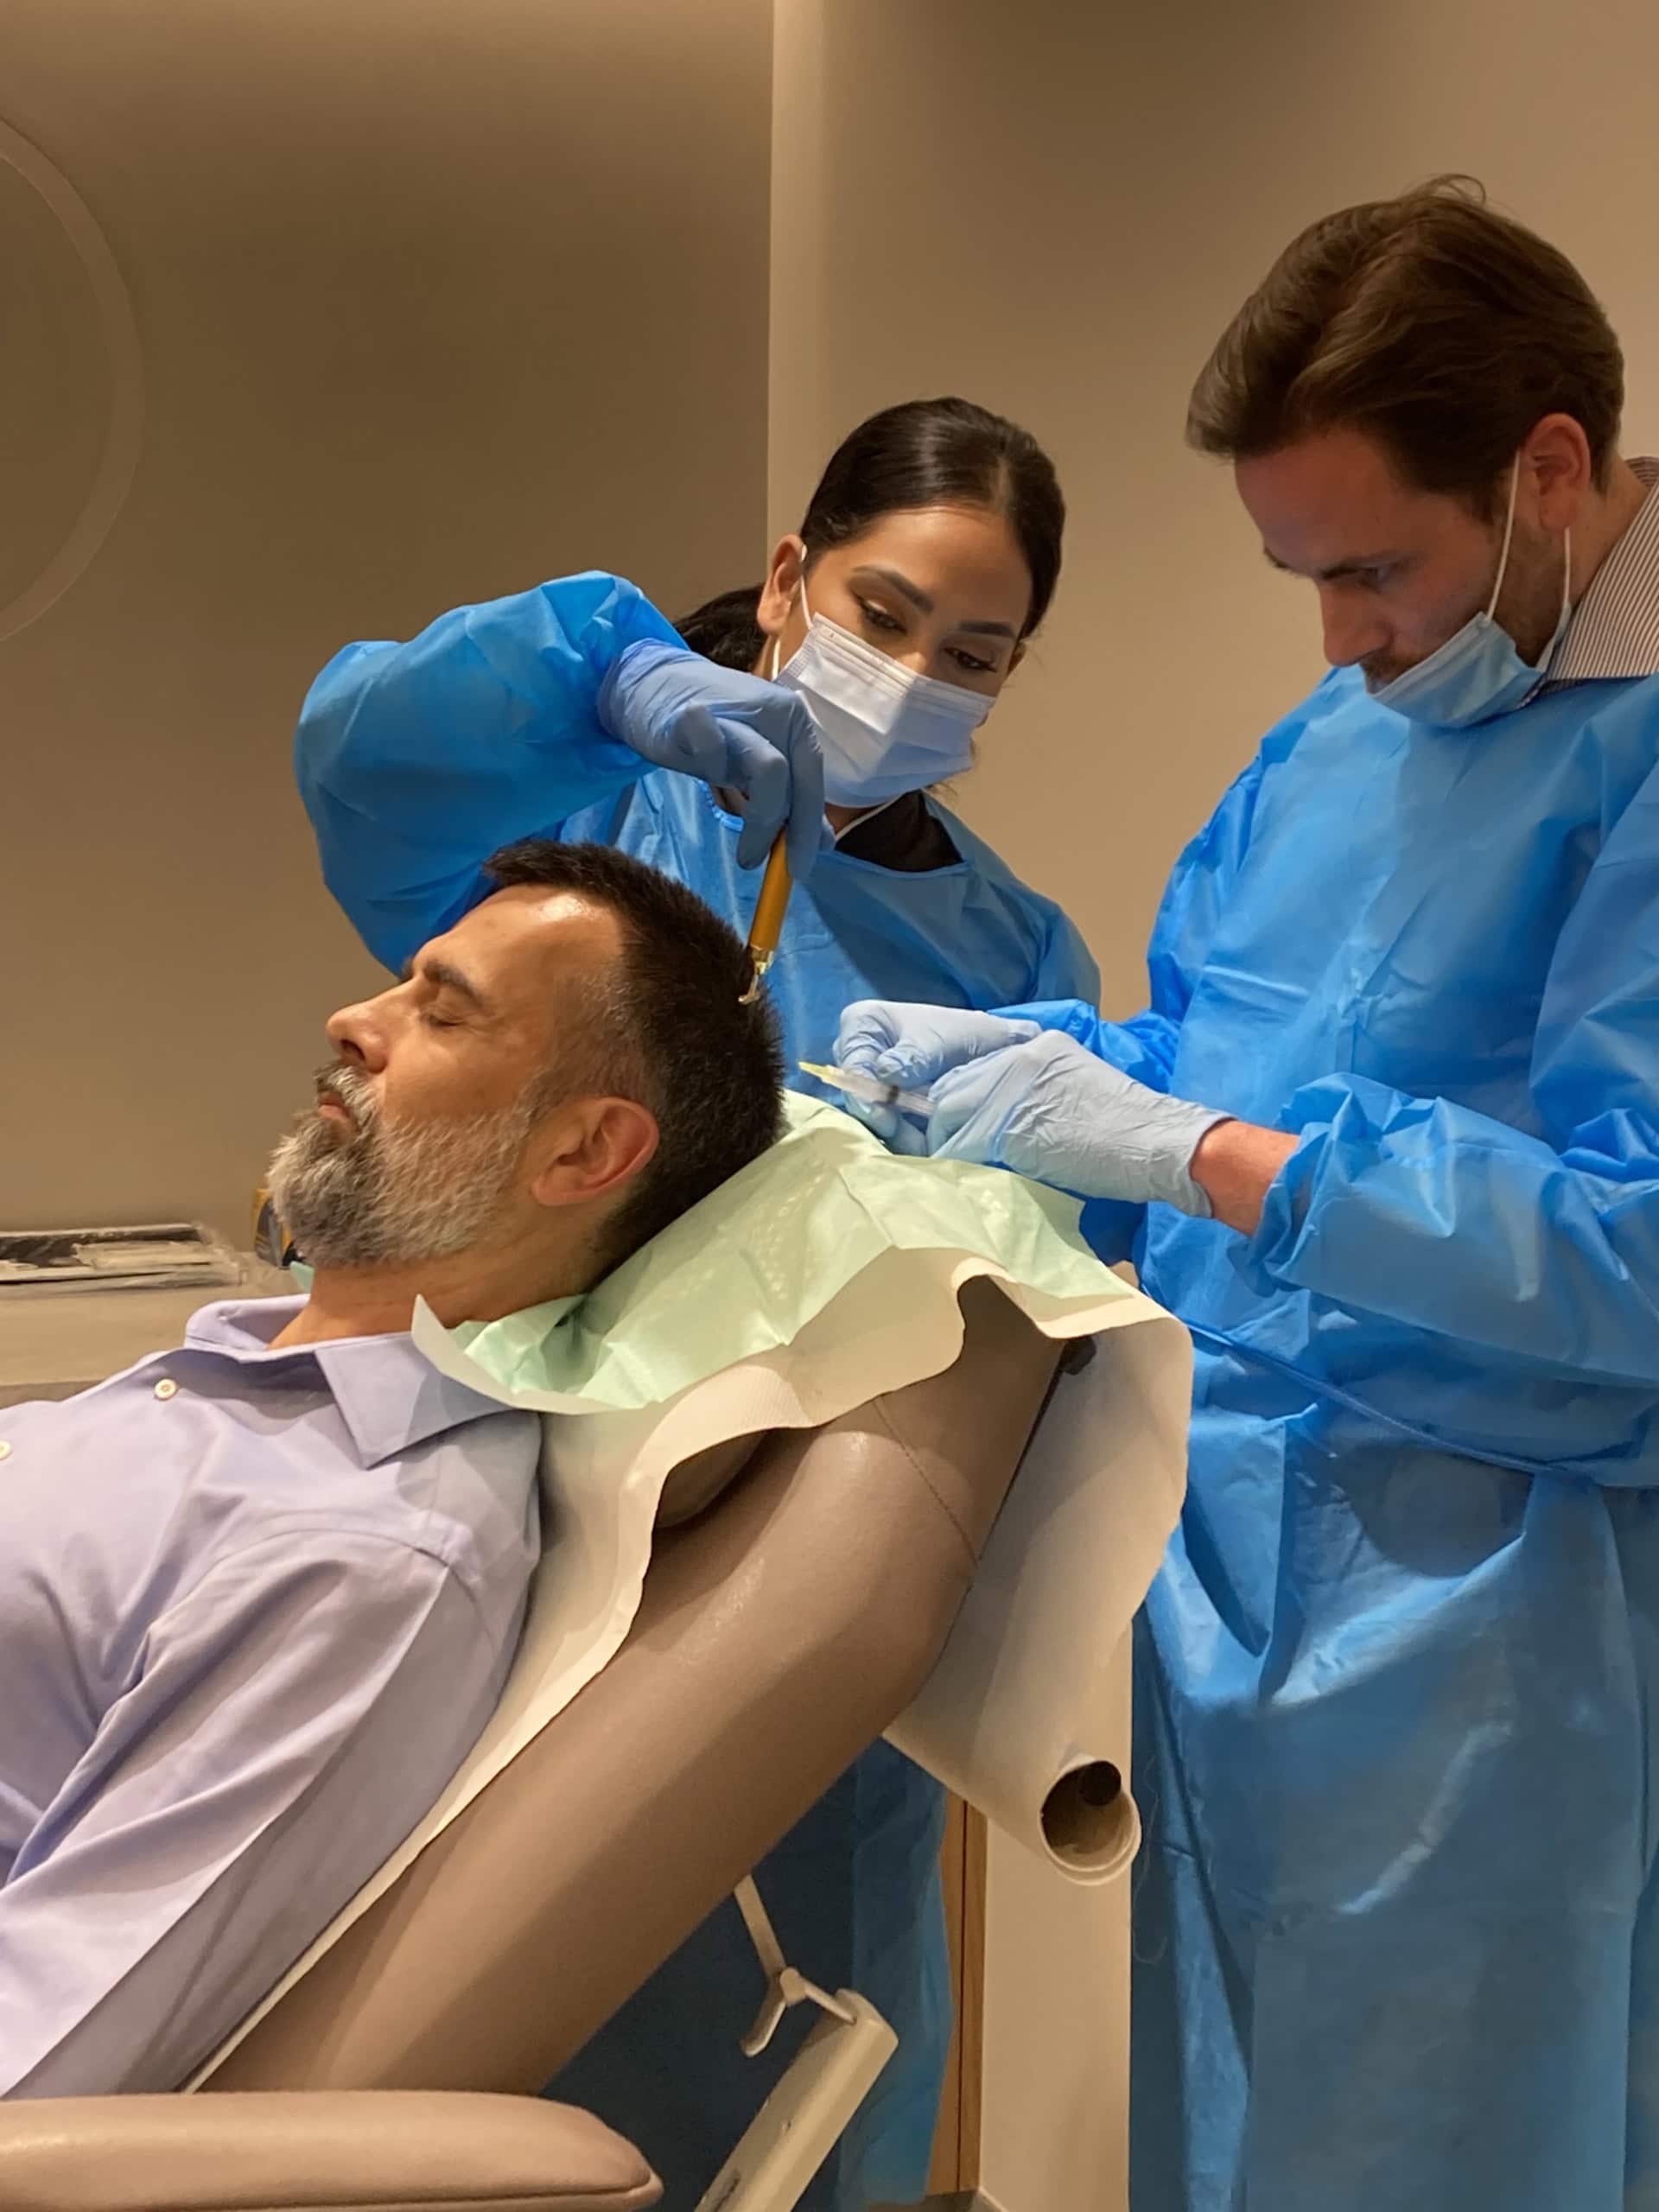
The consultation comes first, and at Ouronyx that means a 3D trichoscopy scan – high-magnification imaging that measures follicle density, hair calibre and scalp inflammation, mapped so it can be repeated later against the same coordinates. It’s the most useful part of the whole process, because it converts “I think it’s getting worse” into a number.
The treatment took around an hour. Local anaesthetic behind the ear, the punches taken – pressure rather than pain – then the processing while you sit there, then the injections across the scalp. The injections are the least pleasant bit and they are still, on a scale of things men willingly pay for, nothing.
Now the honest part, because the brochures all say some version of “no visible marks, return to daily life immediately,” and that isn’t quite my experience.
There was a plaster behind my ear for two days, and two slightly odd red dots where the tissue had been taken, which lingered for a couple of weeks until my hair grew back over them and they disappeared entirely. No scarring, no bandage, no hat, nothing anyone commented on. But “no visible marks” is a stretch – if you have a very short back and sides and you’re in a wedding photo the following weekend, you’d notice them. Book accordingly. Beyond that, no downtime at all. I went back to normal that afternoon.
The results, four months on
Two scans, same clinic, same machine: a baseline on 09/04/26 and a follow-up on 06/08/26. The TrichoLAB system measures four zones – three that were treated, plus the occipital area at the back of the head, which is androgen-resistant and acts as the untreated reference.
The treated areas all moved, and moved hard:
• Crown (vertex): 147 to 203 hairs per cm², up 38%. Average shaft thickness was flat at 40 to 38 microns, but cumulative hair thickness – density and calibre combined – rose from 6.0 to 7.8 mm/cm².
• Frontal: 121 to 175 hairs per cm², up 45%, with average shaft thickness up from 47 to 52 microns.
• Right temple: 128 to 219 hairs per cm², up 71%, with shaft thickness up from 41 to 50 microns and cumulative thickness more than doubling.
The ratio of terminal hairs (thick, mature) to vellus hairs (fine, wispy) improved everywhere: 57% to 60% terminal at the crown, 66% to 74% at the front, 58% to 81% at the temple. That shift matters more to me than the raw counts, because it is precisely the direction androgenetic alopecia runs in, played backwards. The derived Sinclair scores moved with it: 3.3 to 2.8 at the crown, 3.5 to 2.3 at the temple.
I could see it in the mirror before any of this was on a screen, at around the three month mark.
One point to mention: I also started minoxidil this year. The AMT treatment took place on 09/04/26 and I saw visible change within three months. Minoxidil was started later, and minoxidil is broadly accepted to take three to six months before it does anything visible. On timing alone, the early improvement lands in AMT’s column – the minoxidil could not yet have been responsible for it. But I can’t tell you the two are cleanly separable four months out, because they aren’t. Anyone who claims otherwise about their own head is guessing.
AMT vs the alternatives
Four things get sold to men with thinning hair, and they do genuinely different jobs.
• AMT, the stem cell and exosome micrografting treatment. Signals the follicles you still have to keep working, using your own tissue taken, processed and reinjected in a single sitting. Best for early to moderate thinning where the goal is preserving what’s there. One appointment, effectively no downtime, and repeated somewhere between annually and every three years depending on whose protocol you follow.
• A hair transplant (FUE). The only one of the four that physically relocates follicles, and therefore the only one that can fill an area where nothing is growing any more. Best for established bald patches and for designing a hairline. One surgery, six to twelve months to the final result, and a visible recovery measured in days to weeks.
• PRP. Spins the platelets out of your own blood and injects them to signal the follicles – the same broad idea as AMT, but a different payload and no cells in it. Best for early thinning and maintenance. Three to six sessions up front, then top-ups, minimal downtime.
• Off-the-shelf exosome shots. Donor-derived vesicles bought in a vial rather than taken from you, usually sold as a course of several. This is the one to think hardest about, for reasons I’ll come to in the next section.
The first three all put something back that came out of your own body. The fourth doesn’t, and that difference matters more than the marketing around it suggests.
PRP is the comparison most men will actually be weighing, since it’s cheaper and far more widely available. However, micrografts, unlike PRP, contain progenitor cells, “which are key for stimulating hair growth.” PRP delivers growth factors from your own blood; micrografts deliver growth factors plus the cells themselves. Whether that justifies the price gap is a judgement call, but it isn’t marketing – it’s a real difference in what’s going into the syringe.
The exosome question nobody in the industry wants to discuss
“Exosome therapy” has become a catch-all term in aesthetics, and it covers two very different things.
The MHRA regards injected exosomes as medicinal products, and no injectable exosome product currently holds a UK marketing authorisation for aesthetic use; human-derived exosomes are not approved for cosmetic use in the UK or EU. Cambridge pathologists have publicly warned about clinics offering human-cell-derived products injected into other people. If a clinic is offering you exosomes from a bottle – donor-derived, cultured, bought in – you’re entitled to ask what’s in it and under what authority it’s being injected.
AMT is a different proposition. The exosomes involved are the ones already in your own tissue, isolated mechanically and returned to your own scalp in the same appointment. No cultured product, no donor, no vial. That’s the reason I was comfortable with this treatment and wouldn’t be with the other kind. If you take one thing from this piece, take the question: whose cells are these, and when did they leave my body?
How often do you actually need it?

This is where the honest answer and the commercial answer diverge slightly, and it’s worth knowing before you commit to anything.
Ouronyx’s protocol is one session every twelve to eighteen (in most cases) months, each around an hour. Other UK clinics running the same family of technology frame it completely differently: a single treatment, repeated only after two to three years, and only if your loss has visibly progressed. That is an enormous spread for what is essentially the same procedure, and nobody in the industry seems especially keen to reconcile it.
The trial data leans toward the less frequent end. In the published work on the Rigenera system, patients who had a second session six months after the first showed no additional benefit over those who had one. That doesn’t mean top-ups never help – hair loss is progressive, and a treatment that slows it will eventually need repeating – but it does mean the case for two sessions inside the first twelve months is considerably weaker than the case for one session and a rescan.
My own plan is one treatment, measured at six and twelve months, and the repeat decision made on the numbers rather than on the calendar. That’s the real argument for a clinic that scans you properly: you get to buy the second session because the density has slipped, not because a year has elapsed.
What it costs
Ouronyx prices micrografting at £2,950 a treatment, which against a UK transplant – starting around £3,000 and routinely running past £10,000, with a visible recovery – it’s a different order of spend for a different job. Against £15 a month of minoxidil, it’s obviously a lot of money. AMT is a preservation strategy for men who still have something worth preserving, not a rescue.
Would I do it again?

Yes – with two conditions.
First, only alongside the scan. The trichoscopy is what turns this from an expensive act of faith into something you can audit, and I’d be reluctant to have AMT anywhere that couldn’t measure me before and after against the same map. I’d now add one refinement to that: ask for the control area’s numbers alongside your own, every time. It costs nothing, and it is the only thing standing between you and a very flattering percentage.
Second, only as part of the stack rather than instead of it. The evidence base is real but modest – small studies, follow-up typically capped at six months, improvement reported in roughly two-thirds of patients but with quantitative density gains described as small relative to normal measurement fluctuation. One study found a second session six months later added nothing over the first. That’s a promising complementary treatment, not a cure, and the clinics doing this properly say as much.
What it is, genuinely, is the option that didn’t exist a decade ago: something between doing nothing and having surgery. For the men catching themselves in the lift mirror rather than the ones already past it, that’s the only gap that matters.
Stem cell and exosome hair treatment: FAQs
Is AMT a hair transplant?
No. A transplant relocates follicles from the back of your head to the front. AMT takes a few millimetres of tissue and uses the cells within it to stimulate the follicles you already have. Nothing is moved and nothing is added.
How long until you see results from a stem cell and exosome hair treatment?
Reduced shedding is typically reported at six to eight weeks, with visible density changes over three to six months and full results at around six. Mine were visible at around three months.
Is there downtime?
Effectively none. A plaster behind the ear for two days and, in my case, two small red dots at the donor sites that faded over a couple of weeks. No time off, no hat.
Can you combine AMT with minoxidil or finasteride?
Yes, and most protocols assume you will. AMT is generally positioned as complementary to medical therapy rather than a replacement for it – which is also, inconveniently, why it’s hard to attribute results cleanly.
Does it work for women?
Yes. Autologous micrografting protocols are used for both men and women, and the published studies include female patients.
How often do you need AMT repeated?
Ouronyx’s protocol is one session every twelve to eighteen (in most cases) months, each around an hour. Other UK clinics using the same technology treat it as a one-off, repeated only after two to three years if loss progresses. The published trial evidence found no added benefit from a second session at six months, so the honest answer is: have one, get rescanned, and let the density numbers decide when the next one is due.
Disclosure: this treatment was provided for review. The words, the scan results and the opinions are entirely my own.





